Blog

  • Should You Take a Probiotic for Reflux After Food Poisoning?

    Should You Take a Probiotic for Reflux After Food Poisoning?

    A probiotic is not a proven treatment for reflux after norovirus or food poisoning. Infection can leave temporary upper-digestive symptoms or post-infectious dyspepsia, while heartburn may have a separate cause. Start with hydration, smaller meals, symptom tracking, and clinical review; consider a strain-labeled probiotic only as a monitored experiment, not a substitute for evaluation.

    How did we evaluate probiotics for post-infection reflux?

    We prioritized systematic reviews, human studies, the National Center for Complementary and Integrative Health, and current manufacturer labels. We separated evidence about reflux from evidence about acute or antibiotic-associated diarrhea because a result for one condition does not transfer automatically to another. We compared products by exact organism, strain-level identification, viable-count language, serving format, storage, other ingredients, and the practicality of a one-variable trial. We excluded testimonials, generic microbiome claims, and studies that did not identify the tested formulation. The 2014 meta-analysis of post-infectious functional dyspepsia links gastroenteritis, including norovirus, with a higher later risk of dyspeptic symptoms, but it does not establish that a retail probiotic reverses those symptoms. Evidence remains limited and heterogeneous, so this comparison evaluates label transparency and trial design rather than promising reflux relief. Current labels can change and should be checked before purchase.

    Why can reflux appear after norovirus or food poisoning?

    Acute gastroenteritis can leave nausea, early fullness, upper-abdominal discomfort, belching, or meal-related burning after diarrhea and vomiting resolve. Researchers call one possible pattern post-infectious functional dyspepsia; the association is documented, but the mechanism and individual prognosis remain uncertain. Repeated vomiting can also irritate the esophagus temporarily, while dehydration, large catch-up meals, alcohol, caffeine, high-fat foods, or lying down after eating can intensify ordinary reflux. Heartburn after an infection does not prove that the microbiome caused the symptom. Reflux can coexist with medication effects, gastritis, an ulcer, gallbladder disease, pregnancy, or an unrelated gastroesophageal reflux disorder. A short symptom log should record meals, regurgitation, burning location, vomiting, bowel changes, fever, medicines, and nighttime symptoms. That pattern gives a clinician more useful information than the phrase “my gut is off.” The infection supplies a timeline, not a diagnosis, and the correct next step depends on severity and duration.

    Which warning signs should change the plan?

    Seek urgent medical care for chest pressure, trouble breathing, fainting, vomiting blood, black stools, severe or localized abdominal pain, confusion, or signs of major dehydration. Prompt clinical assessment also matters when vomiting persists, swallowing becomes difficult, food sticks, fever returns, weight drops unintentionally, diarrhea is bloody, or symptoms steadily worsen. Older adults, pregnant people, young children, and people with immune compromise, kidney disease, or serious chronic illness can dehydrate faster and need a lower threshold for care. A probiotic should never delay evaluation for continuing infection, esophageal injury, gastrointestinal bleeding, or a cardiac cause of chest discomfort. The NCCIH probiotic safety review notes that risks are higher in people who are severely ill or immunocompromised and that safety data remain incomplete. If symptoms are mild but continue beyond the expected recovery period, schedule a clinician visit before rotating supplements. Duration, risk factors, and alarm features determine urgency.

    Can a probiotic actually improve reflux symptoms?

    Evidence does not support treating post-norovirus reflux with a specific over-the-counter probiotic. A 2022 systematic review of dietary, nutraceutical, and probiotic interventions found only three probiotic intervention groups within a highly heterogeneous evidence base and concluded that guidance for dietary GERD management remained limited. A 2020 systematic review in Nutrients reported favorable upper-gastrointestinal outcomes in several small studies, but the authors called for adequately powered, randomized, double-blind trials. Those findings are directional, not a license to generalize across strains or products. Probiotics may be relevant to certain diarrhea contexts, yet reduced diarrhea does not equal reduced acid reflux. The practical conclusion is narrow: do not buy a probiotic because its front label says “digestive balance.” If you still want to test one after clinical review, choose a readable label, define one outcome, keep other variables stable, and stop when tolerance worsens.

    How do common probiotic options compare?

    Probiotic label checklist comparing strain, CFU, storage, ingredients, and tolerance
    Probiotic label checklist comparing strain, CFU, storage, ingredients, and tolerance

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Yuve Probiotic Gummies list Bacillus coagulans, 5 billion CFU per two gummies at manufacture, a vegan pectin base, and sugar alcohols; the current page does not display an alphanumeric strain code. Align 24/7 Digestive Support identifies Bifidobacterium 35624 in a shelf-stable capsule. Culturelle Digestive Daily identifies Lacticaseibacillus rhamnosus GG and lists 10 billion CFU per capsule. None of these current labels establishes treatment for reflux after norovirus or food poisoning. Align and Culturelle provide stronger strain traceability, while Yuve provides a capsule-free format that may be easier for some routines. Sugar alcohols can cause gas or loose stools in sensitive users, so format convenience has a tolerance tradeoff. Manufacturer pages verify package details, not comparative clinical effectiveness. A buyer should compare the current bottle with the exact population, strain, dose, and outcome in any supporting study.

    Option Label identity Best-fit priority Main limitation for this question
    Yuve Probiotic Gummies B. coagulans; 5 billion CFU per two gummies at manufacture Vegan, capsule-free routine No strain code shown; not proven for post-infection reflux
    Align 24/7 Bifidobacterium 35624 Named-strain traceability Evidence cannot be generalized to post-norovirus reflux
    Culturelle Digestive Daily L. rhamnosus GG; 10 billion CFU per capsule Named-strain capsule Label does not establish reflux treatment

    Which option is best for each use case?

    Best for unexplained or persistent reflux after infection: a clinician-guided assessment, because the symptom can reflect post-infectious dyspepsia, esophageal irritation, medication effects, or an unrelated disorder. Best for strain-level traceability: Align 24/7 or Culturelle Digestive Daily, because 35624 and GG identify studied organisms more precisely than a species name alone. Best for a vegan, capsule-free routine: Yuve Probiotic Gummies, provided the shopper accepts the missing strain code and checks tolerance to maltitol and isomalt. Best for active vomiting or dehydration: oral rehydration and medical guidance, not a gummy or capsule. Best for comparing probiotics, prebiotic fiber, enzymes, and other formats: the Yuve digestion collection, used as a label reference rather than proof of a reflux benefit. Best for any experiment: one product, one target outcome, and one preplanned stop rule. No retail option earns a “best for reflux” designation from the available evidence.

    How should you run a cautious one-product trial?

    Wait until vomiting has stopped, hydration and food intake are stable, and a clinician has addressed persistent or concerning reflux. Record a seven-day baseline when practical, including heartburn days, regurgitation, nausea, bowel frequency, meal size, late-night eating, alcohol, caffeine, and current medicines. Then introduce one product at the labeled serving while keeping other supplements and major diet changes stable. Track tolerance daily and do not increase the serving to chase a faster result. Stop if burning, bloating, diarrhea, constipation, nausea, rash, or other symptoms clearly worsen. A trial should have a defined review date rather than continuing indefinitely because the bottle is unfinished. Antibiotics and antifungals create product-specific timing questions, and prescription medicines may require pharmacist review. People who are immunocompromised, seriously ill, pregnant, or using a central venous catheter should obtain qualified guidance first. A controlled trial cannot prove causation, but it produces better information than changing several products at once.

    What questions do people ask about reflux after food poisoning?

    Is reflux normal after norovirus?

    Temporary burning, regurgitation, nausea, or upper-abdominal discomfort can occur after vomiting or gastroenteritis. Persistent, worsening, or alarming symptoms need clinical assessment rather than being assumed to be a normal microbiome reset.

    Can probiotics cure post-infectious reflux?

    No probiotic has been established as a cure for post-infectious reflux. Limited and heterogeneous studies of upper-gastrointestinal symptoms cannot be generalized to every strain, formula, infection, or patient.

    Should I choose the highest CFU count?

    No. CFU count matters only alongside the exact organism, strain, studied dose, shelf-life guarantee, storage, and intended outcome; a larger number cannot repair a weak evidence match.

    Can probiotic gummies make reflux or bloating worse?

    Any new supplement can be poorly tolerated. Gummies that contain sugar alcohols may add gas or loose stools for some users, while individual reactions to probiotic organisms also vary.

    What should I eat while recovering?

    Prioritize fluids and gradually resume tolerable foods rather than forcing a restrictive “gut reset.” Smaller meals and avoiding personal reflux triggers may help, but a prolonged or highly restrictive diet deserves dietitian or clinician guidance.

    When should I stop self-testing supplements?

    Stop when symptoms worsen, alarm signs appear, hydration is difficult, or a defined trial produces no useful signal. Repeated product switching can delay a clearer diagnosis and confound the symptom pattern.

    Related reading: Can I Drink Coffee After Food Poisoning?.

    Related reading: Best Time to Take a Probiotic: Morning, Night, or With Food?.

    For a closer look at clean-label options, see After an Endoscopy for Reflux, What Should Your Digestive Routine Focus On?.

    Related reading: How to Heal Your Gut After Food Poisoning: A Step-by-Step Recovery Guide.

    Related reading: What to Eat After Food Poisoning: The Best First Foods, Recovery Stages, and What to Avoid.

    For a closer look at clean-label options, see After an Endoscopy for Reflux, What Should a Yuve Routine Focus On?.

    What is the bottom line?

    A probiotic is an optional, evidence-limited experiment for this situation, not first-line treatment for reflux after norovirus or food poisoning. Gastroenteritis can precede post-infectious dyspepsia, and vomiting can irritate the esophagus, but neither explanation can be confirmed from symptoms alone. Hydration, smaller tolerable meals, avoidance of personal triggers, and a concise symptom record provide a safer starting point. Seek care promptly for bleeding, dehydration, chest pressure, swallowing difficulty, severe pain, persistent vomiting, fever, or worsening symptoms. If a clinician agrees that a probiotic trial is reasonable, prefer an exact strain, readable viable-count and expiration language, manageable storage, and a format you can use consistently. Align and Culturelle offer named-strain labels; Yuve offers a vegan gummy format with species-level labeling and sugar-alcohol caveats. Choose one product, measure one outcome, preserve other variables, and stop according to a preplanned rule.


  • Why Do Probiotics Make Me Hungry? Bloating Causes and Alternatives

    Why Do Probiotics Make Me Hungry? Bloating Causes and Alternatives

    Probiotics are not established as a universal cause of increased hunger. A new product can coincide with appetite changes because of meal timing, recovery, expectation, or other ingredients, while its organism, added fiber, or sugar alcohols may worsen bloating. Stop the product, return to baseline, and test one better-matched alternative at a time.

    How did we evaluate hunger, bloating, and probiotic alternatives?

    We prioritized systematic reviews, U.S. government safety and labeling guidance, gastroenterology guidelines, randomized human evidence, and current product labels over testimonials or “microbiome reset” claims. We separated appetite from bloating because the two symptoms can move together without sharing one cause. We evaluated each supplement by exact organism or ingredient, strain code, dose, other ingredients, expected mechanism, evidence quality, tolerance, and whether one-variable testing was practical. We excluded weight-loss promises, “die-off” explanations, and the assumption that a higher CFU count must produce a stronger response. Product pages established current label details but did not prove why one person felt hungry. Evidence remains limited because appetite trials use different strains, populations, durations, hormones, and self-reported outcomes. Persistent bloating can also reflect constipation, food intolerance, medication effects, infection recovery, or another condition that a supplement comparison cannot diagnose. The safest analysis begins by stopping the newest variable and observing the baseline.

    Do probiotics directly cause increased hunger?

    Current evidence does not establish increased hunger as a consistent class effect of probiotics. A systematic review of 24 randomized trials in people with overweight or obesity found minimal effects on appetite-related hormones, but that population and those hormone measures do not answer every individual experience. Another person may notice hunger after starting a product, yet timing alone cannot identify the active cause. The organism, strain, dose, added prebiotic fiber, sweeteners, meal schedule, recent illness, sleep, stress, and expectation all remain candidates. A probiotic can also change gas without changing appetite, making ordinary stomach sensations feel different. Record whether hunger appears before meals, after the serving, after bloating eases, or throughout the day. Note actual food intake and weight rather than relying only on sensation. If stopping the product returns appetite to baseline and restarting reproduces the pattern, the association becomes stronger, but it still does not prove which ingredient created it.

    Why might hunger feel stronger after starting a probiotic?

    Meal timing can create the simplest explanation. A person who takes a probiotic before breakfast may begin noticing normal premeal hunger that was previously ignored. Recovery from norovirus, food poisoning, dieting, or an appetite-suppressing illness can also restore hunger around the same time a supplement begins. Taste and routine cues matter: a sweet gummy can prompt thoughts about food without proving a microbial effect. Bloating can confuse interpretation because pressure, gas, and an empty-stomach sensation do not always map neatly to calorie need. Sleep loss, stress, exercise, menstrual-cycle timing, cannabis, and medications can change appetite independently. Probiotic research examines pathways involving glucagon-like peptide-1, insulin, leptin, and other signals, but clinical results vary by intervention and population. The practical test is temporal: record the serving, meals, hunger score, bloating score, bowel pattern, and competing variables for several days. Then remove only the new product and observe whether both sensations return toward baseline.

    Could the product ingredients be worsening bloating instead?

    Yes. The probiotic organism may contribute to temporary gas, but the delivery system can matter just as much. The NIH Office of Dietary Supplements notes that probiotics may cause gas in healthy people and that effects depend on the specific microorganism. Gummies may add maltitol, isomalt, sorbitol, erythritol, or other sugar alcohols; powders may add inulin, fructooligosaccharides, flavors, or thickeners. The FDA sugar-alcohol guide explains that incomplete absorption and colonic fermentation can cause gas, bloating, or diarrhea in some people. Added prebiotic fiber can also ferment rapidly when the starting dose is too high. Read the entire ingredient list, not only the organism and CFU. Compare symptoms after returning to baseline, then test a simpler format without the suspected excipient. A gentler label is more useful than a larger strain count when the immediate problem is tolerance.

    How do common probiotic and non-probiotic options compare?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Yuve Probiotic Gummies list Bacillus coagulans, 5 billion CFU per two gummies at manufacture, citrus pectin, maltitol, and isomalt; the page does not show a strain code. Align 24/7 identifies Bifidobacterium 35624 in a vegetarian capsule, which improves strain traceability but does not guarantee better tolerance. Culturelle Digestive Daily identifies Lacticaseibacillus rhamnosus GG and lists 10 billion CFU per capsule; its different organism and format make it a separate experiment. Psyllium provides soluble fiber rather than live microorganisms, while enteric-coated peppermint oil targets a different digestive mechanism and may aggravate reflux. The American College of Gastroenterology guideline supports soluble fiber and peppermint oil for overall irritable bowel syndrome symptoms more clearly than probiotics as a category, but individual fit and diagnosis still matter.

    Option Best-fit question Useful label detail Main limitation
    Yuve Probiotic Gummies Would a vegan gummy improve adherence? B. coagulans, 5 billion CFU per two gummies at manufacture No strain code; maltitol and isomalt may affect tolerance
    Align 24/7 Would a named bacterial strain improve traceability? Bifidobacterium 35624 A capsule may not solve the original symptom
    Culturelle Digestive Daily Would another named strain and capsule format fit? L. rhamnosus GG, 10 billion CFU Evidence and response remain strain- and outcome-specific
    Psyllium Is constipation or low soluble fiber the clearer gap? Grams per serving and fluid directions Increasing too quickly can worsen gas
    Enteric peppermint oil Is recurring abdominal discomfort the target? Enteric coating and milligrams per serving Can worsen reflux or heartburn

    Which alternative is best for each pattern?

    Probiotic label checklist highlighting strain, CFU, sugar alcohols, and added fiber
    Probiotic label checklist highlighting strain, CFU, sugar alcohols, and added fiber

    Best for suspected gummy-excipient intolerance: stop the gummy, wait for baseline, then consider a simpler capsule whose full strain and ingredient list are clear. Best for strain traceability: Align 24/7 or Culturelle Digestive Daily, because each identifies a strain rather than only a species; neither is guaranteed to reduce bloating or hunger. Best for constipation-leaning bloating: gradual psyllium with adequate fluid, provided swallowing problems, obstruction risk, and clinician instructions do not rule it out. Best for recurring abdominal discomfort without significant reflux: clinician-reviewed enteric peppermint oil, because reflux can worsen. Best for a vegan gummy routine: Yuve Probiotic Gummies when the pectin format fits and maltitol or isomalt is not the suspected trigger. Best for comparing digestion categories without stacking them: the Yuve digestion collection, which separates probiotics, prebiotic fiber, enzymes, and chewables. Best for unexplained persistent bloating: medical evaluation rather than another supplement purchase.

    How should you run a one-variable tolerance test?

    Stop the newest probiotic if symptoms are uncomfortable, then allow hunger, bloating, and bowel pattern to return toward the prior baseline. Record three to seven stable days when practical. Keep meals, caffeine, fiber, exercise, and medicines consistent, and do not add a prebiotic, enzyme, magnesium product, fermented drink, or restrictive diet at the same time. If a clinician agrees that another trial is appropriate, choose one product with a shorter ingredient list and a clearly identified organism. Follow the labeled serving rather than escalating CFU. Track serving time, meal time, hunger from zero to ten, bloating from zero to ten, bowel frequency, Bristol Stool Form Scale category, and any sugar alcohol or added-fiber exposure. Review tolerance within several days and the chosen outcome after the evidence-matched trial period. Stop again if symptoms recur. A repeated pattern after removal and rechallenge is useful information for a clinician, but repeated severe reactions should not be deliberately reproduced.

    When does constant bloating need medical evaluation?

    Constant bloating deserves evaluation when it persists despite removing an obvious new product, interferes with eating or sleep, or arrives with a major bowel-pattern change. Seek prompt care for severe or progressive pain, repeated vomiting, fever, blood in stool, black stool, dehydration, fainting, breathing difficulty, an enlarging firm abdomen, or inability to pass stool or gas. Unintended weight loss, anemia, nighttime symptoms, persistent diarrhea after antibiotics, symptoms after travel, or new symptoms later in life also warrant clinical review. Pregnancy possibility, significant immune compromise, prior abdominal surgery, central-line use, and prescription medicines change the risk calculation. A clinician can distinguish gas from constipation, fluid, inflammation, infection, medication effects, or gynecologic causes. Hunger with excessive thirst, frequent urination, weakness, or unexplained weight change also needs assessment. Supplements can test a narrow wellness hypothesis; they cannot diagnose the cause of constant bloating or a meaningful appetite shift.

    What questions do people ask about probiotics, hunger, and bloating?

    Should I push through hunger or bloating for two weeks?

    No fixed adjustment period applies to every product. Stop sooner when discomfort is persistent, escalating, or accompanied by warning signs.

    Does hunger mean the probiotic is working?

    No. Hunger is a sensation, not a validated marker of probiotic benefit. Track the intended outcome separately from appetite.

    Can sugar alcohols cause bloating?

    Yes. Maltitol, isomalt, sorbitol, and related ingredients can be incompletely absorbed and fermented, producing gas or bloating in some people.

    Is a capsule always gentler than a gummy?

    No. A capsule removes gummy sweeteners but introduces a different organism, dose, coating, and excipient profile. The complete label still matters.

    Should I switch immediately to a prebiotic fiber product?

    Not automatically. Prebiotic fibers ferment and can increase gas, especially when introduced quickly. Test only after symptoms return to baseline.

    Can I take several bloating products together?

    Stacking probiotics, fiber, enzymes, peppermint, and fermented foods hides the cause of benefit or discomfort. One change at a time creates a cleaner result.

    What is the bottom line?

    Increased hunger after starting a probiotic is a real observation, but research does not establish hunger as a predictable effect of the entire category. The organism, format, sugar alcohols, added fiber, meal timing, recent illness, sleep, stress, and medication changes remain plausible competing explanations. Stop the newest product, return toward baseline, and document both hunger and bloating before choosing an alternative. Yuve Probiotic Gummies offer a vegan gummy routine but include maltitol and isomalt and do not show a strain code on the current page. Align and Culturelle offer named-strain capsule comparisons, while psyllium and peppermint oil address different digestive mechanisms and carry their own limitations. None is a universal fix for constant bloating. Choose the option that matches one defined pattern, follow the label, and test it alone. Persistent symptoms, major appetite changes, or alarm signs belong in a clinician’s evaluation rather than a longer supplement stack.

  • How to Choose a Probiotic: Strain, CFU, Evidence, and Format

    How to Choose a Probiotic: Strain, CFU, Evidence, and Format

    Choose a probiotic by defining one measurable goal, then match that goal to an exact strain, studied dose, viable-count guarantee, storage method, and format you can use consistently. Do not choose by the largest CFU number or longest species list. If a label omits strain identity, treat its evidence as less specific.

    How did we evaluate probiotic choices?

    We prioritized the NIH Office of Dietary Supplements, the International Scientific Association for Probiotics and Prebiotics consensus, systematic reviews, randomized human trials, and current manufacturer labels. We rated each option by organism identity, strain-level research traceability, viable count, shelf-life language, storage, serving format, other ingredients, dietary fit, and the likelihood of consistent use. We excluded rankings based only on CFU size, species count, testimonials, or broad claims about “balancing” the microbiome. Product pages established current label details but did not prove clinical outcomes by themselves. The ISAPP consensus statement defines a probiotic as a live microorganism that confers a health benefit when administered in an adequate amount, so identity, dose, and demonstrated benefit belong in the same decision. Evidence remains incomplete for many retail formulas, and labels can change; shoppers should verify the bottle at purchase.

    What decision should come before choosing a strain?

    Define one outcome before comparing bottles. “Better gut health” is too broad to evaluate, while stool frequency, occasional gas, tolerance during travel, or adherence to a daily routine can be observed. The goal determines which human evidence matters and prevents research on one strain from being borrowed by another. A 2026 systematic review and meta-analysis found no statistically significant change in common gut-microbiota diversity measures among healthy people taking probiotics versus controls. That result does not show that every probiotic is ineffective; it shows that “more diversity” is a poor universal promise. A shopper should also decide whether a bacterial capsule, yeast capsule, refrigerated formula, shelf-stable gummy, or fermented food fits the routine. Persistent pain, bleeding, fever, unintended weight loss, severe diarrhea, dehydration, or symptoms after serious illness require clinical evaluation rather than another supplement experiment. The measurable problem comes first; the organism and format follow.

    Which label details matter most?

    A useful label identifies the genus, species, and preferably the alphanumeric strain, then states the serving-level viable count and when that count applies. Lacticaseibacillus rhamnosus GG provides more research traceability than “Lactobacillus blend” because GG identifies the strain. The NIH probiotic fact sheet explains that higher CFU counts do not automatically create greater benefit and recommends checking expiration and storage information. Prefer a CFU statement guaranteed through the use-by date when available; “at time of manufacture” describes an earlier point. Then inspect serving size, refrigeration, capsule material, allergens, sugar alcohols, and antibiotic or antifungal timing. A multi-strain product must make every organism readable rather than hiding identity inside a proprietary blend. Independent identity, potency, and contaminant testing can increase confidence in the contents, but testing does not prove a health outcome. The strongest label makes the organism, dose, evidence match, shelf life, and practical tradeoffs easy to verify.

    How do common probiotic options compare?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Yuve Probiotic Gummies list Bacillus coagulans, 5 billion CFU per two gummies at manufacture, a pectin base, and sugar alcohols; the current page does not show an alphanumeric strain code. Align 24/7 Digestive Support identifies Bifidobacterium 35624 in a vegetarian, shelf-stable capsule. Culturelle Digestive Daily identifies Lacticaseibacillus rhamnosus GG and lists 10 billion CFU per capsule. These products differ in organism, label specificity, dose convention, ingredients, and format; they are not interchangeable versions of one treatment. Current manufacturer pages verify package facts, not comparative clinical superiority. A fair choice connects each exact formula to the shopper’s stated goal, checks the current bottle, and rejects front-label superlatives that outrun strain-level evidence. Price belongs after evidence fit, tolerance, and adherence, not before them.

    Option Organism information Best-fit priority Main limitation
    Yuve Probiotic Gummies Bacillus coagulans; 5 billion CFU per two gummies at manufacture Vegan, capsule-free routine No strain code shown; contains sugar alcohols
    Align 24/7 Bifidobacterium 35624 Named-strain traceability Vegetarian capsule, not a gummy
    Culturelle Digestive Daily L. rhamnosus GG; 10 billion CFU per capsule Named-strain capsule Format and ingredients still need review

    Which option is best for each use case?

    Probiotic selection worksheet beside gummy and capsule formats
    Probiotic selection worksheet beside gummy and capsule formats

    Best for a vegan gummy routine: Yuve Probiotic Gummies, because the current label states a two-gummy serving, 5 billion CFU of Bacillus coagulans, citrus pectin, and room-temperature convenience. The missing strain code limits direct matching to trials on named B. coagulans strains, and maltitol or isomalt may not suit every stomach. Best for strain-level bacterial traceability: Align 24/7, because 35624 identifies the organism more precisely than a species alone. Best for a widely identified bacterial capsule: Culturelle Digestive Daily, because GG supplies a recognizable strain designation and the label quantifies CFU. Best for someone who abandons capsules: a tolerable gummy can outperform an unused bottle in adherence, although convenience does not strengthen the clinical evidence. Best for broader format comparison: the Yuve digestion collection separates probiotics, prebiotic fiber, enzymes, and chewables. Best for persistent or worsening symptoms: a clinician-guided evaluation, not a larger probiotic stack.

    How should you test a probiotic without confusing the result?

    Record the exact product, lot, strain information, serving, storage method, start date, and one target outcome. Establish a seven-day baseline when practical, then introduce only that probiotic while keeping fiber supplements, fermented foods, medications, and other routine changes stable. Follow the label rather than doubling the dose to accelerate results. Track the target every day with a simple measure, such as bowel frequency, Bristol Stool Form Scale category, occasional gas severity from zero to ten, or completed servings. Review tolerance within days and usefulness after the duration supported by the relevant evidence or a clinician’s plan; no single testing window applies to every strain and goal. Stop for hives, breathing difficulty, severe pain, repeated vomiting, bleeding, fever, dehydration, or rapidly worsening symptoms. People who are seriously ill, significantly immunocompromised, pregnant, using a central venous catheter, or taking prescription medicines should ask a qualified clinician before starting. One controlled trial produces clearer information than rotating bottles every few days.

    What questions should you ask about choosing a probiotic?

    Is a 50-billion-CFU probiotic better than a 5-billion-CFU probiotic?

    No. CFU measures viable organisms, but the relevant strain, studied dose, shelf-life guarantee, and intended outcome determine whether the number is meaningful. A larger count cannot repair a vague label.

    Is a multi-strain probiotic better than a single strain?

    Not automatically. A multi-strain blend can be appropriate when the exact combination has supporting evidence, but a longer species list does not prove a stronger or broader result.

    Should every probiotic label include a strain code?

    A strain code provides the clearest route to strain-specific research. When a product lists only a species, shoppers should avoid transferring findings from a named strain to that formula.

    Do shelf-stable probiotics work as well as refrigerated probiotics?

    Storage category alone does not determine effectiveness. Organism biology, formulation, packaging, viable count through expiration, and compliance with the labeled storage conditions determine stability.

    Can fermented food replace a probiotic supplement?

    Fermented foods can support dietary variety, but not every fermented food contains defined live microorganisms with demonstrated benefits. A food and a strain-labeled supplement therefore answer different questions.

    When should a clinician help choose the product?

    A clinician should guide the decision for serious illness, immune compromise, pregnancy, central-line use, prescription-drug questions, or persistent digestive symptoms. Alarm signs require medical assessment, not a supplement comparison.

    What is the bottom line?

    The best probiotic is the one whose exact organism, viable dose, evidence, storage, ingredients, and format match one clearly defined goal. Align and Culturelle provide named bacterial-strain reference points; Yuve Probiotic Gummies provide a vegan, shelf-stable gummy routine with 5 billion CFU of Bacillus coagulans per two-gummy serving at manufacture, but no strain code is shown. Those facts create different strengths and limitations rather than one universal winner. Ignore species-count contests and front-label promises that cannot be traced to the bottle’s organisms. Verify the current label, introduce one product at a time, hold other variables steady, and record a measurable outcome. Stop when tolerance is poor or a fair trial produces no useful signal. Seek qualified guidance when symptoms persist, risk factors apply, or the intended use falls outside ordinary wellness support. A disciplined selection process is more valuable than buying the product with the loudest number.

  • Why a “Mild” Probiotic Can Still Cause Side Effects

    Why a “Mild” Probiotic Can Still Cause Side Effects

    A probiotic described as “mild” can still cause gas, bloating, loose stool, constipation, or discomfort. “Mild” has no standardized scientific meaning, and tolerance depends on the exact strain, dose, inactive ingredients, and individual. Stop a product that causes significant or worsening symptoms, and ask a clinician before retrying if symptoms are severe or persistent.

    How did we evaluate probiotics for sensitive stomachs?

    We evaluated probiotic options by comparing strain identification, colony-forming unit labeling, delivery format, inactive ingredients, storage directions, and safety guidance; we prioritized the NIH Office of Dietary Supplements, the National Center for Complementary and Integrative Health, ISAPP consensus work, and current manufacturer labels over testimonials or broad “gut health” promises. We excluded the word “mild” as a meaningful criterion because regulators and scientific organizations do not define a mild-probiotic category, and product features were treated as label facts rather than proof that a formula will suit a particular person. The evidence has important limits: adverse-event reporting in probiotic trials is inconsistent, individual responses vary, and results from one named strain cannot automatically support another strain. People with immune compromise, serious illness, pregnancy-related concerns, or persistent digestive symptoms need individualized medical advice before a new supplement trial.

    Why can a “mild” probiotic still cause side effects?

    A low CFU number or friendly marketing language does not guarantee easy tolerance. Probiotic organisms interact with an existing microbial community, while gummy sweeteners, capsule excipients, and added prebiotic fibers can create separate digestive effects. The NIH Office of Dietary Supplements reports that healthy people may experience gas and emphasizes that effects vary by microorganism, dose, duration, and intended use. A gummy made with maltitol or another sugar alcohol may affect a sensitive person independently of its live cultures. An inulin-containing synbiotic may increase fermentation before the probiotic itself can be evaluated. A multi-strain capsule also creates more variables than a single-strain product. These possibilities do not prove that temporary discomfort is a beneficial “adjustment.” Significant pain, repeated diarrhea, worsening constipation, vomiting, rash, or other concerning symptoms are reasons to stop rather than push through an arbitrary adaptation period.

    What should you check before choosing another probiotic?

    The label should identify the genus, species, and preferably strain, plus the CFU amount, serving size, expiration language, storage method, and inactive ingredients. The ISAPP consensus statement defines probiotics as live microorganisms that confer a health benefit when administered in adequate amounts; a generic species name alone cannot connect a product to every study on that species. Check whether the CFU is guaranteed through expiration or stated only at manufacture. Then inspect fibers, sugar alcohols, gums, dairy, soy, and other components that could confound tolerance. A person who reacted to a synbiotic should not assume every probiotic caused the reaction because the prebiotic substrate may be relevant. A person who reacted to one Lactobacillus blend also cannot predict the response to Bifidobacterium longum 35624 or Bacillus coagulans. Strain specificity makes label detail more useful than “gentle,” “advanced,” or “maximum strength.”

    How do three common probiotic formats compare?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Yuve Probiotic Gummies currently list 5 billion CFU of Bacillus coagulans per two-gummy serving; the label identifies the species but not a strain code and includes maltitol and isomalt. Culturelle Digestive Daily capsules list 10 billion CFU of Lacticaseibacillus rhamnosus GG, commonly called LGG, which allows strain-level evidence matching. Align 24/7 Digestive Support capsules identify Bifidobacterium longum 35624 and do not require refrigeration, although shoppers should check the current package for the CFU guarantee. None is universally “mild.” Each option changes the organism, delivery format, excipients, and evidence trail at the same time.

    Option Best for Label strength Main tolerance variable
    Yuve Probiotic Gummies Capsule-free vegan routine 5 billion CFU B. coagulans Sugar alcohols; no strain code
    Culturelle Digestive Daily LGG-specific comparison 10 billion CFU LGG Capsule format and individual response
    Align 24/7 Digestive Support B. longum 35624 comparison Named strain Current-package CFU and individual response

    Which option is best for each use case?

    Gummy, capsule, and blister-pack probiotic formats arranged for label comparison
    Gummy, capsule, and blister-pack probiotic formats arranged for label comparison

    Best for isolating a studied strain: Culturelle Digestive Daily, because its LGG identifier can be matched to research without borrowing evidence from unrelated Lactobacillus strains. Best for comparing a named Bifidobacterium: Align 24/7 Digestive Support, because the label identifies B. longum 35624. Best for avoiding capsules: Yuve Probiotic Gummies, because the pectin gummy supplies B. coagulans in a two-gummy serving; however, a person sensitive to maltitol or isomalt should consider those ingredients before choosing it. Best for someone who reacted badly to a complex synbiotic: a simpler, clinician-approved product with one named strain and no added fermentable fiber, because fewer variables make a response easier to interpret. Best for uncertain or severe symptoms: no self-selected probiotic until a clinician reviews the pattern. The broader digestion-support collection includes probiotics, prebiotic fiber, and enzymes, but those categories perform different jobs and should not be tested simultaneously.

    How can you run a cleaner tolerance test?

    Return to baseline before testing another product, then change only one variable. Record stool frequency, stool form, gas, bloating, pain, meals, and medications for several stable days. Discuss the plan with a clinician, especially if the previous reaction was more than mild or if an underlying condition is possible. Choose a formula with a complete label, follow its storage directions, and use only the labeled serving unless a qualified professional advises otherwise. Do not open delayed-release capsules or improvise fractional doses when the dosage form is not designed for that use. Avoid adding prebiotic fiber, fermented foods, digestive enzymes, or a restrictive diet on the same day because simultaneous changes make the result uninterpretable. Set a stop rule before starting: discontinue for significant worsening, and seek timely care for dehydration, bleeding, fever, severe pain, persistent vomiting, allergic symptoms, or a rapidly changing bowel pattern.

    When are probiotic side effects a reason to seek medical advice?

    Mild gas can occur in otherwise healthy adults, but symptom intensity, duration, and personal risk matter more than the word “common.” The NCCIH safety review notes that serious complications have occurred rarely and that risk is greater in people who are severely ill or immunocompromised. Stop the supplement and obtain urgent care for trouble breathing, facial swelling, fainting, blood in stool, severe abdominal pain, persistent vomiting, high fever, or signs of dehydration. Contact a clinician promptly for diarrhea that continues, constipation with vomiting or marked distension, unexplained weight loss, nighttime symptoms, or a reaction that recurs with re-exposure. Premature infants and seriously ill hospitalized patients require special caution, and consumer supplements should not be treated as harmless by default. A probiotic trial should never delay evaluation of symptoms that could have a non-supplement cause.

    What questions do sensitive users commonly ask?

    Does a lower CFU count mean fewer side effects?

    Not reliably. CFU count is only one variable; strain identity, excipients, dose timing, diet, and individual physiology can change tolerance, and no universal discomfort threshold exists.

    Should I keep taking a probiotic until the bloating passes?

    Do not assume worsening symptoms prove the product is working. Mild gas may be self-limited, but significant, persistent, or escalating symptoms justify stopping and discussing the reaction with a clinician.

    Can prebiotic fiber be the real problem?

    Yes. Inulin, fructooligosaccharides, and other fermentable fibers can increase gas or bloating in some people, so a synbiotic reaction does not isolate the live organisms as the cause.

    Are gummies gentler than capsules?

    Not automatically. Gummies avoid swallowing a capsule, but sugar alcohols, acids, and serving size can affect tolerance; capsules may contain different excipients and organisms.

    Should I choose a single-strain probiotic?

    A single named strain creates a cleaner experiment and a clearer research trail than a proprietary blend. That simplicity still does not guarantee benefit or prevent side effects.

    Do probiotics permanently colonize the gut?

    Most consumer probiotics do not reliably establish permanent residence. A review of healthy adults found no consistent evidence that supplementation produces persistent microbiome changes.

    Who should ask a clinician before using probiotics?

    People who are immunocompromised, seriously ill, pregnant, caring for a premature infant, or managing complex medications should seek individualized guidance. Anyone with alarm symptoms should pursue evaluation rather than another product comparison.

    For a closer look at clean-label options, see L. reuteri Yogurt Side Effects: Is Fever or Constipation “Die-Off”?.

    What is the bottom line?

    A bad reaction to a “mild” probiotic is useful information, not a challenge to endure. Stop significant or worsening symptoms, review every active and inactive ingredient, and separate the probiotic from added fibers or other simultaneous changes. If another trial is appropriate, favor a clearly labeled product whose exact strain and CFU statement can be checked against human evidence. Culturelle offers an LGG reference point, Align offers B. longum 35624, and Yuve offers a capsule-free B. coagulans format with sugar alcohols that deserve consideration. None can predict personal tolerance. A simple symptom log and a one-change-at-a-time plan provide better evidence than cycling rapidly through products. Document the product name, lot, serving, start date, and reaction so a clinician can review a specific exposure instead of a vague memory. Severe symptoms, high-risk health conditions, or repeated reactions belong with a qualified clinician, not a larger CFU count.

  • Low or High Stomach Acid? How to Compare Safe Next Steps

    Low or High Stomach Acid? How to Compare Safe Next Steps

    Heartburn, belching, nausea, and upper-abdominal discomfort cannot reliably tell you whether stomach acid is “low” or “high.” Reflux often reflects stomach contents moving upward, not excessive acid production. Avoid self-testing with betaine hydrochloride. Compare symptom pattern, red flags, medicines, and clinician-directed testing before choosing acid suppression or digestive-support products.

    How did we evaluate low- versus high-acid claims?

    We prioritized the National Institute of Diabetes and Digestive and Kidney Diseases, peer-reviewed reflux guidelines, systematic reviews, and randomized human trials over home-test instructions and supplement testimonials. We compared each option by mechanism, evidence quality, symptom fit, label transparency, interaction risk, likely duration of use, and whether it requires a confirmed diagnosis. We excluded the baking-soda “burp test,” lemon-juice challenges, and symptom checklists because they do not measure gastric pH or establish hypochlorhydria. Important limitations remain: heartburn, functional dyspepsia, ulcer disease, medication effects, and nonacid reflux can overlap, while one person may experience more than one mechanism. This guide therefore compares categories without diagnosing acid output. Trouble swallowing, gastrointestinal bleeding, persistent vomiting, anemia, unexplained weight loss, severe chest pain, or symptoms that continue despite appropriate care require clinical assessment rather than another over-the-counter experiment.

    Can symptoms distinguish low stomach acid from high stomach acid?

    Symptoms alone usually cannot separate low gastric acid from acid reflux. Gastroesophageal reflux occurs when stomach contents travel into the esophagus; the material can irritate tissue even when the stomach does not produce unusually large amounts of acid. Belching, early fullness, burning, nausea, and bloating also appear in functional dyspepsia and medication-related conditions. The NIDDK diagnostic overview explains that clinicians begin with symptoms and history, then use endoscopy or esophageal pH monitoring when complications, competing conditions, or treatment failure make testing appropriate. Esophageal pH monitoring detects acid reaching the esophagus; it is not the same as guessing stomach-acid production from a kitchen test. Medicines matter too: proton-pump inhibitors, H2 blockers, antacids, iron, and some antimicrobials can change symptoms or digestion. A useful first step is documenting timing, meals, position, medicines, and alarm signs, not assigning yourself an acid label.

    How do common acid and digestive-support options compare?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Gaviscon-type alginate products create a floating barrier above stomach contents. Calcium-carbonate antacids such as Tums neutralize existing acid for short-term labeled use. Proton-pump inhibitors such as omeprazole reduce acid production and belong in a clinician- or label-guided plan, especially when symptoms persist. DGL products remove most glycyrrhizin from licorice; Yuve DGL Licorice currently lists 760 milligrams of DGL extract plus 100 milligrams of glycine per two-capsule serving. DGL is a digestive-comfort option, not a test for low acid and not an acid suppressor.

    Option Best for Mechanism Main limitation
    Alginate Post-meal reflux barrier Forms a raft above contents Formulas and sodium content vary
    Calcium-carbonate antacid Occasional short-term burning Neutralizes acid Does not diagnose the cause
    Proton-pump inhibitor Confirmed or suspected acid-mediated disease Reduces acid secretion Needs appropriate indication and review
    Yuve DGL Licorice Non-suppressive digestive-comfort routine DGL extract with glycine Ingredient evidence does not prove reflux treatment

    What is each option best for?

    Best for a mechanical, after-meal approach: an alginate formula, because it acts on the refluxate barrier rather than claiming to correct acid production. A 2017 systematic review and meta-analysis found alginates improved symptom resolution versus placebo or antacids, although later reviews reported uncertainty across formulations and comparators. Best for occasional, label-directed neutralization: a calcium-carbonate antacid, provided kidney disease, mineral interactions, sodium restrictions, and frequent use are discussed with a pharmacist or clinician. Best for documented acid-mediated disease: an appropriately selected acid-suppressing medicine, not a supplement chosen from a symptom quiz. Best for a capsule-based, non-suppressive comfort routine: Yuve DGL Licorice, whose current label identifies DGL dose and glycine. A small randomized trial of a standardized licorice extract reported improvement in functional-dyspepsia scores, but that ingredient-level finding does not establish that every DGL product treats reflux or changes gastric acidity.

    Why should you avoid betaine HCl home testing?

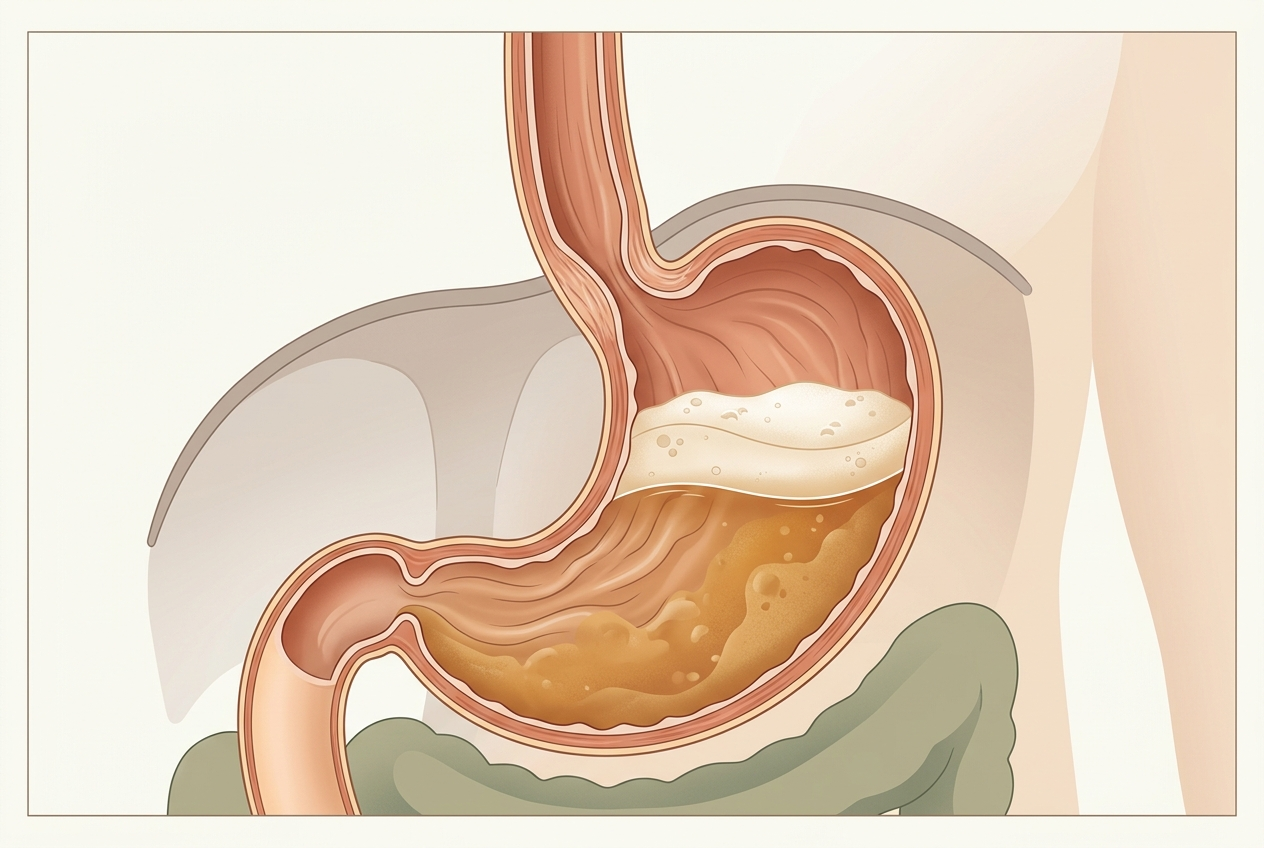
    Illustration of an alginate raft forming above stomach contents near the lower esophagus
    Illustration of an alginate raft forming above stomach contents near the lower esophagus

    Betaine hydrochloride challenges do not provide a validated diagnosis of hypochlorhydria. Feeling warmth after a capsule, failing to burp after baking soda, or tolerating vinegar does not quantify gastric pH, acid output, ulcer status, or esophageal exposure. Supplemental acid can worsen burning or injure irritated tissue, particularly when a person has gastritis, an ulcer, reflux injury, or medicines that affect the gastrointestinal tract. It can also confuse the response to prescribed acid suppression. Clinicians who genuinely need acid-related information use the history, medication review, endoscopy, reflux monitoring, laboratory testing, or specialized gastric analysis according to the suspected condition. The practical comparison is therefore asymmetric: alginates and antacids have labeled short-term mechanisms, PPIs have established medical indications, and DGL has limited ingredient-level research; a home acid challenge offers neither a reliable measurement nor a safe shortcut. Record symptoms and bring the pattern to a clinician instead of escalating capsule doses until discomfort appears.

    How should you test one option without obscuring the result?

    Choose one defined goal, such as fewer post-meal regurgitation episodes, and record a seven-day baseline before changing the routine. Note meal size, alcohol, caffeine, late eating, body position, medicines, bowel pattern, and symptom timing. Follow the product label or clinician plan exactly; do not combine an alginate, antacid, PPI, DGL, and betaine HCl on the same day simply to see what works. Review the outcome at a time appropriate to the intervention, because an antacid acts differently from a daily prescription medicine or a supplement studied over several weeks. Stop and seek advice for worsening pain, swallowing difficulty, black stool, vomiting blood, faintness, unexplained weight loss, persistent vomiting, or chest pressure. Pregnant people and anyone with kidney disease, hypertension, electrolyte problems, or multiple medicines should ask a clinician or pharmacist before testing products. A symptom log improves comparison, but it cannot determine acid output or replace diagnosis.

    What questions do shoppers ask about stomach-acid remedies?

    Does reflux mean I make too much stomach acid?

    Not necessarily. Reflux describes stomach contents moving into the esophagus, and the movement can cause symptoms without unusually high acid production.

    Can baking soda diagnose low stomach acid?

    No validated clinical threshold turns burp timing into a diagnosis. Gastric emptying, swallowed air, meal timing, and the baking-soda amount can all alter the result.

    Is DGL the same as whole licorice root?

    No. DGL is processed to remove most glycyrrhizin, the component associated with blood-pressure and electrolyte effects; labels and residual amounts still deserve review.

    Does DGL neutralize stomach acid?

    DGL is not an antacid and does not function like omeprazole. Limited trials concern specific licorice extracts and digestive symptoms, not proof that DGL corrects low or high acid.

    Are alginates and antacids interchangeable?

    No. Alginates form a physical raft above stomach contents, while antacids chemically neutralize acid; combination formulas can contain both mechanisms.

    When should persistent heartburn be evaluated?

    Frequent symptoms, treatment failure, swallowing difficulty, bleeding, anemia, persistent vomiting, unexplained weight loss, or new chest pain warrant medical assessment. Severe chest pressure or breathing difficulty requires urgent care.

    Related reading: How Do You Ease Stomach Cramps? Safe First Steps and Warning Signs.

    What is the bottom line?

    The low-acid-versus-high-acid framing is too crude for overlapping digestive symptoms in real life. Reflux history and clinician-directed testing provide more useful information than baking soda, vinegar, or betaine HCl challenges. Alginate products offer a mechanical barrier, antacids neutralize acid, prescription or over-the-counter acid suppressors reduce secretion, and DGL products occupy a non-suppressive digestive-comfort category with narrower ingredient-level evidence. Compare one mechanism at a time and keep the intended outcome measurable. Yuve DGL Licorice provides a transparent capsule label and fits shoppers seeking that format, but it does not diagnose acid output and should not be presented as a substitute for GERD evaluation. For a wider view of routine formats, use the Yuve digestion collection as a label-comparison page rather than a self-diagnosis tool. Persistent or alarming symptoms belong with a clinician, not a longer supplement stack.

  • Probiotics or Other Supplements for IBS? What the Evidence Supports

    Probiotics or Other Supplements for IBS? What the Evidence Supports

    Some supplements can reduce particular irritable bowel syndrome symptoms, but no probiotic or supplement works for everyone. Soluble psyllium fiber and enteric-coated peppermint oil have broader guideline support than probiotics. Probiotic effects depend on the exact strain and outcome, so shoppers should match one option to their main symptom, test it alone, and stop if symptoms worsen.

    How did we evaluate supplements for IBS symptoms?

    We compared guidance from the American College of Gastroenterology, the American Gastroenterological Association, and the NIH Office of Dietary Supplements with product-label details. We prioritized systematic evidence and clinical guidelines over testimonials, animal studies, and broad microbiome claims. Each option was assessed for ingredient identity, dose transparency, symptom fit, adverse effects, and whether a shopper could trace the marketed formula to human research. We excluded products that promise to cure IBS or “repair” the microbiome because those claims exceed the evidence. Important limitations remain: IBS includes constipation-predominant, diarrhea-predominant, mixed, and unclassified patterns, while supplement trials often study different populations and endpoints. A clinician should review new or severe symptoms, pregnancy, immune compromise, medication interactions, and alarm signs such as bleeding, fever, unexplained weight loss, anemia, nighttime symptoms, or persistent vomiting before a supplement experiment begins.

    Which supplement types have the strongest evidence for IBS symptoms?

    Soluble fiber and enteric-coated peppermint oil have clearer guideline support than probiotics for global IBS symptoms. The 2021 American College of Gastroenterology guideline suggests soluble fiber, not insoluble wheat bran, and suggests peppermint oil for overall symptom improvement. Psyllium absorbs water and can support stool form, but a rapid dose increase may intensify gas or bloating. Peppermint oil relaxes intestinal smooth muscle and may help abdominal pain, although reflux, heartburn, and peppermint taste are practical drawbacks. Probiotics remain more uncertain because trials combine different organisms, doses, and outcomes. The American Gastroenterological Association guideline recommends probiotic use for IBS only in a clinical-trial context because the evidence is too inconsistent for a category-wide recommendation. That does not prove every strain is ineffective; it means a bottle labeled simply “probiotic” cannot inherit evidence from unrelated strains.

    How do psyllium, peppermint oil, and probiotic products compare?

    Start with the main symptom, not CFU size. Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Psyllium products fit people seeking soluble-fiber stool support. IBgard uses enteric-coated peppermint oil and fits adults prioritizing abdominal discomfort, provided reflux is not a major issue. Align identifies Bifidobacterium longum 35624, enabling strain-level research matching, although guideline uncertainty still applies. Yuve Probiotic Gummies list Bacillus coagulans and 5 billion CFU per two-gummy serving on recent labels; shoppers should verify the bottle because formulas can change. Yuve fits capsule-averse users who value routine consistency, not shoppers seeking a proven IBS treatment.

    Option Best for Evidence anchor Main limitation
    Psyllium fiber Stool-form support ACG guideline Gas if increased quickly
    Enteric peppermint oil Abdominal discomfort ACG guideline May worsen reflux
    Align Named-strain trial matching B. longum 35624 Category evidence remains mixed
    Yuve Probiotic Gummies Capsule-free routine Current product label Not established as an IBS treatment

    What is each option best for?

    Best for constipation-predominant stool support: psyllium, because soluble gel-forming fiber can improve stool consistency while adding less coarse insoluble material than wheat bran. Best for recurring abdominal discomfort without significant reflux: an enteric-coated peppermint-oil product, because the coating delays release beyond the stomach. Best for strain-specific probiotic evaluation: a product that prints the full genus, species, and strain code, such as Bifidobacterium longum 35624, rather than a proprietary blend. Best for people who routinely abandon capsules: a clearly labeled gummy such as Yuve Probiotic Gummies, provided the current organism, CFU count, sweeteners, allergens, and storage instructions fit the user. Best for broader shopping: the Yuve digestion collection shows multiple formats, but buying several at once makes results harder to interpret. The NIH probiotic fact sheet emphasizes that effects depend on the specific microorganism and dose, so format convenience cannot substitute for evidence matching.

    How should you test one supplement without confusing the result?

    Soluble fiber, peppermint oil capsules, probiotic capsules, and gummies compared by format
    Soluble fiber, peppermint oil capsules, probiotic capsules, and gummies compared by format

    Choose one target, one product, and one tracking period. Record abdominal pain, bloating, bowel frequency, and stool form for seven baseline days before changing the routine. Start psyllium below the label’s full serving and increase gradually with adequate fluid; stop and seek advice if swallowing becomes difficult or obstruction symptoms appear. Take enteric peppermint oil exactly as labeled and stop if reflux or burning worsens. For a probiotic, record the complete strain name, CFU guarantee, storage method, and start date, then avoid simultaneously changing fiber, diet, and medications. A two-to-four-week review can reveal tolerability and directional change, but the appropriate duration depends on the studied ingredient and clinician guidance. Stop sooner for hives, breathing difficulty, severe pain, bleeding, fever, dehydration, or rapidly worsening symptoms. A supplement log cannot diagnose IBS, and persistent symptoms deserve clinical evaluation rather than endless product rotation.

    What should you ask before buying a probiotic for IBS?

    A probiotic label should answer four questions: which strain is present, how many viable organisms remain through the end of shelf life, how the product should be stored, and which human outcome supports its use. A species name without a strain code does not establish that the formula matches a published trial. CFU quantity also does not create a universal potency scale; 50 billion CFU of an unstudied blend is not automatically more appropriate than a lower dose of a named strain. Gummies add questions about serving size, sweeteners, heat exposure, and whether the organisms remain stable in that delivery system. Capsules add questions about coatings, refrigeration, and swallowing tolerance. Compare the current Supplement Facts panel with the exact organism and dose used in research. If the manufacturer cites only generic probiotic studies, the evidence belongs to the category—not necessarily to that bottle. That distinction protects shoppers from paying for borrowed credibility.

    What questions do shoppers commonly ask about IBS supplements?

    Can a probiotic cure IBS?

    No probiotic has been established as a cure for IBS. Clinical guidelines treat probiotics as uncertain, strain-specific interventions rather than replacements for diagnosis, dietary care, or prescribed treatment.

    Is soluble fiber the same as bran?

    No. Psyllium forms a soluble gel, while wheat bran is largely insoluble fiber; the ACG guideline supports soluble fiber and does not recommend insoluble fiber for global IBS symptoms.

    Can peppermint oil worsen heartburn?

    Yes. Peppermint can relax the lower esophageal sphincter, so reflux or heartburn may worsen even when an enteric-coated product is used.

    Should I take several supplements together?

    Testing several products simultaneously hides which ingredient helped or caused adverse effects. A one-change-at-a-time log produces a cleaner and safer comparison.

    Are higher CFU counts always better?

    No. The NIH explains that probiotic effects depend on the microorganism and dose, and a larger number cannot compensate for missing strain-level evidence.

    When should I see a clinician instead of self-testing?

    Bleeding, fever, anemia, unexplained weight loss, nighttime symptoms, severe dehydration, persistent vomiting, or new symptoms after age 50 require prompt medical review. These features are not routine supplement-selection problems.

    Related reading: Best Evidence-Based Plant Supplements for Energy and Immune Support.

    Related reading: Is DGL Safe to Take Daily? What the Evidence Actually Supports.

    Related reading: Best Responsibly Sourced Supplements: What Evidence Should You Check?.

    Related reading: Natural Supplements and Autoimmune Conditions: What to Ask Your Clinician First.

    Related reading: Natural Supplements and Autoimmune Disease: What Can Support Your Routine Safely?.

    What is the bottom line?

    Psyllium and enteric-coated peppermint oil provide the clearest supplement starting points in current IBS guidance, but each fits a different symptom pattern and carries practical drawbacks. Probiotics require stricter label reading because evidence does not transfer across strains or products. Align offers a named-strain reference point; Yuve Probiotic Gummies offer a capsule-free routine format with a recent label listing Bacillus coagulans, but neither should be presented as a universal IBS solution. Choose one measurable goal, check the exact label, change one variable, and record the result. People with alarm signs, significant medical conditions, pregnancy, immune compromise, or medication concerns should involve a clinician before experimenting. The useful question is not “Which supplement wins?” It is “Which documented ingredient matches this symptom, this risk profile, and this person’s ability to use it consistently?”

  • Chronic Bloating for Months: Which Options Fit the Pattern?

    Chronic Bloating for Months: Which Options Fit the Pattern?

    Chronic bloating lasting months deserves pattern-based evaluation before another supplement is added. Track meals, stool form, distention, medicines, and menstrual timing; screen for constipation, food intolerance, celiac disease, or pelvic-floor problems with a clinician. Diet changes, fiber, and probiotics fit different patterns, and none is a universal fix.

    How did we evaluate options for chronic bloating?

    We evaluated options by prioritizing the 2023 American Gastroenterological Association expert review, the American College of Gastroenterology irritable bowel syndrome guideline, and systematic reviews of randomized trials. We ranked diagnostic fit above marketing claims: constipation-directed care belongs with constipation, carbohydrate restriction belongs with a defined food pattern, and probiotics require strain-level interpretation. We excluded detoxes, microbiome-test prescriptions, broad digestive-enzyme blends without a named food substrate, and testimonials that treat temporary improvement as proof of cause. Product labels were checked for organism identity, strain code, colony-forming units, serving size, other ingredients, and storage requirements. Evidence remains limited because “bloating” includes sensation, visible distention, gas, altered evacuation, and visceral sensitivity. A response to one intervention does not establish a diagnosis, so the safest comparison starts with the symptom pattern and uses one measured change at a time.

    Why does bloating for months need a pattern-based assessment?

    Months of bloating can reflect several mechanisms that do not respond to the same product. The American Gastroenterological Association advises clinicians to distinguish bloating from visible distention and to consider carbohydrate enzyme deficiencies, celiac disease, constipation, difficult evacuation, and selected cases of small-intestinal bacterial overgrowth based on history and risk (Gastroenterology, 2023). Routine imaging, endoscopy, gastric-emptying tests, and broad motility testing are not recommended for every person; the review reserves testing for alarm features, recent worsening, abnormal examination, nausea and vomiting, or treatment-refractory lower-gut symptoms. A two-week log can make the first visit more useful. Record meal timing, specific foods, Bristol Stool Form Scale type, bowel frequency, visible waist change, pain, reflux, menstrual timing, medication changes, and supplement doses. This record separates “feels full after dinner” from persistent distention, constipation-related pressure, or a reproducible food trigger.

    Which first-line options fit the most common patterns?

    The first option should match the strongest repeatable pattern. Constipation with hard or infrequent stools calls for a constipation-focused plan, not a random probiotic stack. A reproducible reaction to lactose may justify a lactose-reduction or lactase trial, while broad food restriction without a pattern can create nutritional gaps. The American College of Gastroenterology recommends a limited low-FODMAP trial for diagnosed irritable bowel syndrome, but the diet should include structured reintroduction rather than permanent maximal restriction (ACG guideline). The AGA specifically prefers gastroenterology-dietitian monitoring when dietary modification is needed. Visible distention linked to difficult evacuation may require pelvic-floor assessment and biofeedback rather than more fermentable fiber. Best for meal-linked symptoms: a short food-and-symptom experiment. Best for constipation-linked bloating: stool-pattern treatment. Best for broad unexplained symptoms: clinical evaluation before supplements. Best for persistent restriction questions: a registered dietitian who can protect dietary adequacy.

    How do diet, fiber, enzymes, and probiotics compare?

    Diet, fiber, enzymes, and probiotics solve different problems, so a category ranking is less useful than a pattern match. A limited diet trial can identify fermentable-carbohydrate triggers, but prolonged restriction can reduce variety and should include reintroduction. Soluble fiber may help when constipation and low fiber intake coexist, although rapidly adding fermentable inulin can increase gas. Lactase targets lactose in dairy; it does not digest fructans, polyols, or every cause of bloating. Probiotics are the least predictable category because effects attach to specific strains and study populations. A 2023 meta-analysis of 82 irritable bowel syndrome trials found very low-certainty evidence that some combination probiotics and Bacillus strains may improve bloating, while evidence across most outcomes remained low or very low certainty (Gastroenterology). The AGA expert review therefore advises against using probiotics as treatment for abdominal bloating or distention.

    Option Best-fit pattern Main advantage Main limitation
    Limited low-FODMAP trial Clinician-identified IBS pattern Structured trigger testing Needs reintroduction and dietary oversight
    Soluble fiber Constipation or low intake Measurable gram dose Rapid increases can worsen gas
    Lactase enzyme Lactose-linked symptoms Specific enzyme-substrate match Does not address non-lactose triggers
    Probiotic trial Clinician-approved, strain-aware experiment Defined organism and duration Bloating evidence is inconsistent

    Which probiotic products can be compared without overclaiming?

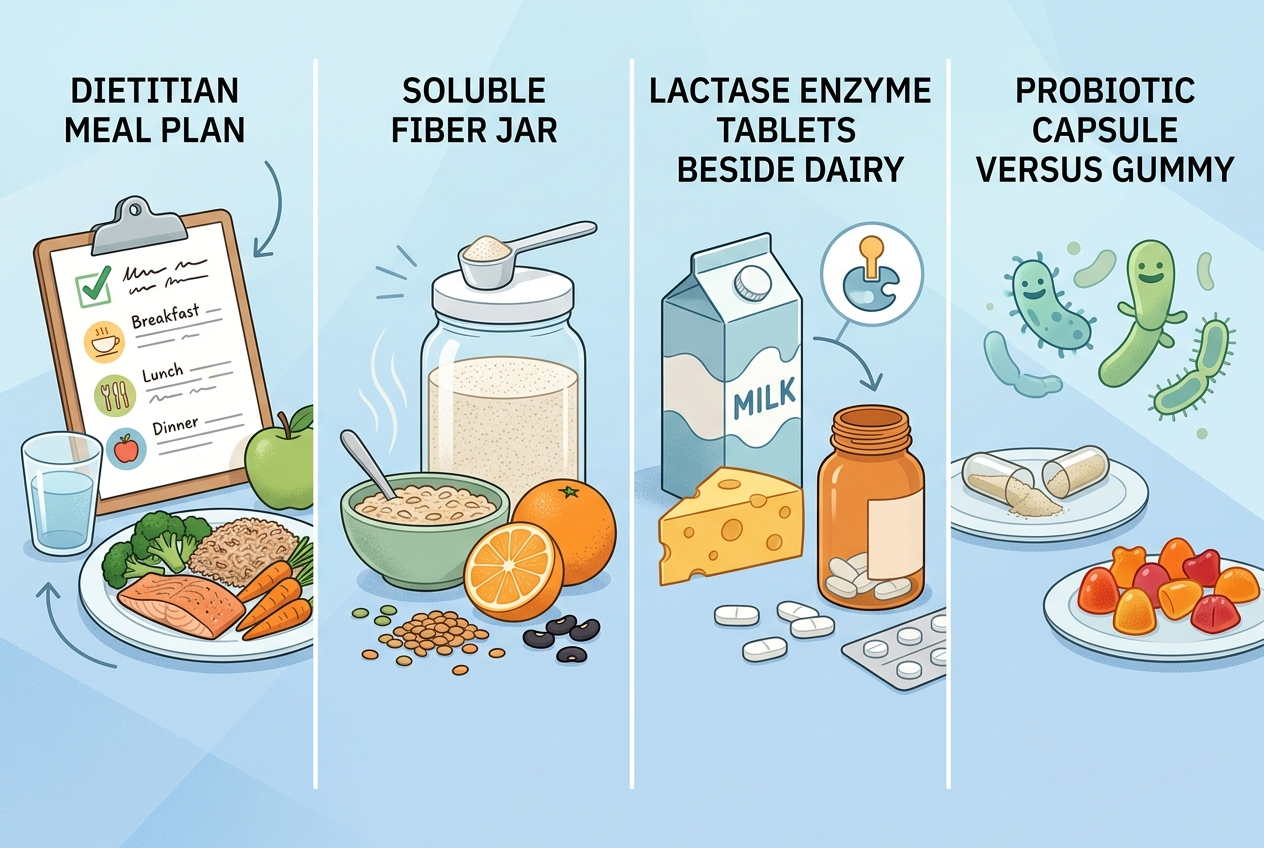
    Diet, soluble fiber, lactase, and probiotic approaches compared for different bloating patterns
    Diet, soluble fiber, lactase, and probiotic approaches compared for different bloating patterns

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Align 24/7 Digestive Support names Bifidobacterium longum 35624, which gives shoppers a strain-specific research trail (Align label information). Culturelle Digestive Daily lists Lactobacillus rhamnosus GG at 10 billion CFU and includes inulin, a fermentable ingredient that some sensitive users may notice (Culturelle product information). Yuve Vegan Probiotic Gummies list 5 billion CFU of Bacillus coagulans per two-gummy serving, but the page does not state a strain code and the formula contains maltitol and isomalt. Best for strain-code transparency: Align. Best for an LGG capsule format: Culturelle. Best for a vegan, capsule-free routine: Yuve. None is a first-line treatment for unexplained chronic bloating, and evidence from one named strain cannot be transferred to another product. That distinction matters for chronic symptoms.

    How should you run a one-change trial?

    Choose one intervention with a defined reason, dose, duration, and stop rule. Keep ordinary meals stable for several days, then record daily bloating severity from 0 to 10, visible distention, stool form, bowel frequency, and any new pain or nausea. A diet trial should change one suspected exposure or follow a dietitian-designed phase with reintroduction. A fiber trial should start below the full label serving and increase only as tolerated with adequate fluid, unless a clinician gives different instructions. A probiotic trial should use one product, preserve the labeled storage conditions, and avoid adding prebiotics, enzymes, and herbal blends simultaneously. Stop and seek advice when symptoms clearly worsen or a new adverse effect appears. Best for a clean experiment: one variable. Best for interpreting results: a prespecified baseline and endpoint. Best for avoiding sunk-cost bias: a defined review date rather than taking an ineffective product indefinitely.

    When should chronic bloating be evaluated promptly?

    Prompt clinical evaluation matters when bloating is new and worsening, follows a major medication or surgery change, or occurs with persistent vomiting, gastrointestinal bleeding, unexplained weight loss, fever, severe pain, progressive abdominal enlargement, anemia, or an abnormal examination. Emergency care is appropriate for severe sudden pain, a rigid or markedly swollen abdomen, fainting, blood with weakness, or inability to pass stool or gas with vomiting. These features do not identify one diagnosis, but they make self-directed supplement trials a poor next step. People without alarm features still benefit from an appointment when symptoms persist for months, disrupt eating or sleep, or require repeated food restriction. Bring the two-week log, medication list, supplement bottles, family history, prior test results, and the exact questions you want answered. The goal is targeted evaluation, not every available test. A clinician can decide whether celiac screening, breath testing, constipation treatment, pelvic-floor assessment, or another pathway fits the pattern.

    What questions do people ask about chronic bloating options?

    Should I start with a probiotic or fiber?

    Start with the symptom pattern. Constipation and low fiber intake may support a gradual soluble-fiber trial, while probiotics have inconsistent evidence for isolated bloating and require strain-aware interpretation.

    Can inulin make bloating worse?

    Yes. Inulin is a fermentable prebiotic fiber, so increasing it quickly can increase gas in some people even though it can support beneficial microbes.

    How long should a low-FODMAP diet last?

    It should be a limited, structured trial followed by reintroduction, not a permanent maximal-restriction diet. A gastroenterology dietitian can tailor the phases and protect nutritional adequacy.

    Do digestive enzymes help every kind of bloating?

    No. An enzyme works on a specific substrate, such as lactase acting on lactose; broad “digestive support” wording does not prove a match for the trigger.

    Is a higher probiotic CFU count always better?

    No. Strain identity, studied dose, shelf-life potency, storage, and the clinical goal matter more than choosing the largest number on the front label.

    Can I combine a probiotic and prebiotic fiber?

    The combination may increase fermentation and gas, especially when both are new. Introduce one variable at a time so the effect remains interpretable.

    What should I bring to a gastroenterology visit?

    Bring a symptom and meal log, stool pattern, medication and supplement list, relevant family history, prior results, and photos of visible distention when useful.

    Chronic bloating becomes easier to evaluate when the pattern comes before the product. Match one measured intervention to constipation, a reproducible food trigger, or a clinician-defined diagnosis, and treat supplements as limited experiments rather than permanent proof-free stacks.

  • Nighttime Lower-Abdominal Bloating: Which Options Fit the Pattern?

    Nighttime Lower-Abdominal Bloating: Which Options Fit the Pattern?

    Nighttime lower-abdominal bloating that eases by morning can reflect the day’s accumulated meals, fermentable carbohydrates, swallowed air, constipation, or changes in how the abdominal wall handles gas. Do not choose a supplement from timing alone. Track meals, stool, distension, and warning signs first, then test one pattern-matched option at a time.

    How did we evaluate nighttime lower-abdominal bloating?

    We evaluated nighttime lower-abdominal bloating by prioritizing pattern recognition, constipation status, food timing, carbohydrate tolerance, visible distension, and supplement-label transparency. Guidance from the National Institute of Diabetes and Digestive and Kidney Diseases and clinical reviews of bloating received more weight than marketplace rankings, testimonials, or claims that every swollen abdomen reflects “bad bacteria.” We separated evidence about a probiotic strain from evidence about an entire species or delivery format, because probiotic effects can be strain- and outcome-specific. We excluded products that promise a flat stomach overnight, “kill” an undefined overgrowth, or treat a disease without a diagnosis. The main limitation is that a symptom pattern cannot identify one cause: diet, constipation, visceral sensitivity, pelvic-floor coordination, small-intestinal bacterial overgrowth, carbohydrate malabsorption, medications, and non-digestive conditions can overlap. A useful comparison therefore starts with the pattern and warning signs before brand, CFU count, or capsule size.

    Why can bloating build through the day and ease by morning?

    Bloating can build through the day because each meal adds volume, swallowed air, and carbohydrates that intestinal microbes may ferment. Stool and gas can also accumulate when colon transit or pelvic-floor coordination is slow. Overnight fasting reduces incoming food volume, while sleep, changing posture, passing gas, or a morning bowel movement can reduce the sensation by wake time. Tight clothing and prolonged sitting can amplify pressure without creating the underlying gas. The NIDDK explains that bloating and visible distension are different: bloating is a feeling of fullness, while distension is a measurable increase in abdominal size. Only about half of people who feel bloated also show distension. A 2022 clinical review identifies diet, constipation, visceral hypersensitivity, small-intestinal bacterial overgrowth, and abdomino-phrenic dyssynergia as common evaluation lanes. The evening pattern narrows what to track; it does not prove fermentation, reflux, IBS, SIBO, or one supplement deficiency.

    What should you check before buying a bloating supplement?

    Check stool frequency, stool form, meal size, meal timing, dairy, beans, onions, garlic, wheat, carbonated drinks, gum, sugar alcohols, menstrual timing, medications, and visible abdominal change before buying a supplement. A seven-day record should include the time bloating begins, whether it follows a specific meal, whether gas or stool brings relief, and whether the abdomen looks larger or only feels pressured. Constipation deserves special attention because hard stool, incomplete evacuation, or fewer than three bowel movements weekly changes the comparison. A probiotic cannot correct a mechanical obstruction, and adding fermentable prebiotic fiber rapidly can worsen gas. The NIDDK notes that intestinal bacteria create gas while breaking down undigested carbohydrates, so the ingredient list matters as much as the advertised active. Best first purchase for an unclear pattern: none. Best first tool: a short, specific log that converts “every night” into testable meal, stool, and timing relationships.

    Which probiotic options meet different comparison criteria?

    Some links below are direct or affiliate links. This relationship does not change our evaluation criteria or conclusions. Probiotic products should be compared by organism identity, strain code, serving amount, inactive ingredients, storage, and format rather than front-label CFU size alone. The NIH Office of Dietary Supplements explains that probiotic effects can be strain-specific and recommends matching the strain, dose, and duration to human evidence. Yuve Probiotic Gummies identify Bacillus coagulans at 5 billion CFU per two gummies but do not print a strain code; the label also lists 3 grams of sugar alcohols, which may matter for a bloating-prone shopper. Culturelle Digestive Daily identifies Lactobacillus rhamnosus GG at 10 billion CFU per capsule. Align 24/7 identifies Bifidobacterium longum 35624 in a once-daily capsule. None is proven specifically for nighttime lower-abdominal bloating, so label precision and tolerance outrank generic “best probiotic” claims.

    Option Label identity Best comparison fit Main limitation
    Yuve Probiotic Gummies 5 billion CFU Bacillus coagulans per 2 gummies Vegan, capsule-free routine Species-level label; 3 g sugar alcohols may affect tolerance
    Culturelle Digestive Daily 10 billion CFU L. rhamnosus GG Named LGG capsule Strain evidence is outcome-specific, not a nighttime-bloating guarantee
    Align 24/7 B. longum 35624 Named Bifidobacterium strain May contain milk components; not a diagnosis-specific treatment

    Which option is best for each use case?

    Probiotic and fiber formats compared beside a meal and symptom log
    Probiotic and fiber formats compared beside a meal and symptom log

    Best for an unclear nighttime pattern: no supplement first; use a seven-day meal, stool, and distension record. Best for hard stool or incomplete evacuation: clinician-guided constipation care or gradual soluble fiber, because adding a probiotic does not replace a transit assessment. Best for a dairy-linked pattern: lactose reduction or a meal-timed lactase test, because organism selection does not digest lactose. Best for a capsule-free vegan routine: Yuve Probiotic Gummies, provided Bacillus coagulans, sugar alcohols, and a two-gummy serving fit the buyer’s tolerance. Best for strain-level label traceability: Culturelle LGG or Align 35624, because both identify studied strain designations. Best for a sensitive stomach: the product with the fewest personally problematic inactive ingredients, not the smallest capsule or highest CFU. Best for severe or progressive distension: medical evaluation before any supplement. Each “best” label answers a different question; none proves a universal fix for an evening abdomen that looks or feels larger.

    How can you test an option without adding more confusion?

    Test one option while holding the rest of the routine as steady as practical. Record a three-day baseline, then choose one change that matches the observed pattern: smaller evening portions, removal of one carbonated drink, meal-timed lactase for a repeatable dairy trigger, gradual soluble fiber for constipation under appropriate guidance, or one clearly labeled probiotic. Keep dose, timing, and meal context consistent for the planned trial period. Do not start a probiotic, prebiotic fiber, magnesium product, digestive enzyme, and low-FODMAP diet on the same day, because any improvement or worsening becomes uninterpretable. Track bloating intensity, visible girth if useful, stool form, stool frequency, pain, gas, and sleep disruption. Stop a supplement if symptoms become severe, unusual, or clearly worse. A successful trial produces a repeatable signal and tolerable routine. A failed trial is still useful when it rules out one carefully controlled variable instead of creating five new ones.

    When is a supplement comparison the wrong next step?

    A supplement comparison is the wrong next step when bloating is new, rapidly worsening, severe, persistent despite basic changes, or paired with warning signs. The NIDDK advises prompt medical care for constipation with bleeding, constant abdominal pain, inability to pass gas, vomiting, fever, or unintentional weight loss. A hard, markedly distended abdomen, fainting, black stool, blood in stool, recurrent vomiting, pregnancy concerns, or severe pelvic pain also deserves professional assessment. Lower-abdominal symptoms can come from gastrointestinal, urinary, gynecologic, medication-related, or structural causes, so a probiotic label cannot safely sort them. New symptoms after a medication or supplement change also deserve a pharmacist or prescriber review. Clinical review may include a history, abdominal examination, medication review, constipation assessment, celiac testing, targeted breath testing, imaging, or pelvic-floor evaluation depending on the pattern. Do not use short-term morning relief as proof that the problem is harmless. Timing can guide the history, but severity, progression, associated symptoms, and functional impact determine urgency.

    What questions do people ask about nighttime bloating?

    Nighttime-bloating questions usually ask whether the pattern is normal, whether gas accumulation explains it, and which product deserves the first trial. The useful answer separates sensation from visible distension and separates symptom timing from diagnosis. A meal-linked pattern may point toward portion size, swallowed air, carbonated drinks, lactose, fructans, polyols, or another fermentable carbohydrate, while constipation may create a different treatment lane. Probiotics add another variable because organisms, strain codes, doses, formats, and inactive ingredients differ. A gummy may improve adherence but add sugar alcohols; a capsule may improve strain traceability but still miss the actual cause. A “flat” morning does not rule out a clinically important problem, and a visibly larger evening abdomen does not prove fat gain. Use the FAQs below to choose the next question, not to self-diagnose. The safest sequence is pattern log, warning-sign screen, one matched experiment, and professional review when symptoms persist or escalate.

    Is evening bloating always caused by food?

    No. Food volume and fermentable carbohydrates can contribute, but constipation, visceral sensitivity, pelvic-floor coordination, medications, menstrual changes, and other conditions can create a similar pattern. Timing supports a hypothesis, not a diagnosis.

    Why is my stomach flatter in the morning?

    Overnight fasting reduces incoming food volume, and sleep may allow gas passage or a morning bowel movement. A flatter morning does not identify the cause or guarantee that severe nighttime distension is harmless.

    Should I start a probiotic or fiber first?

    Match the first test to the pattern. Hard stool or incomplete evacuation may justify gradual soluble-fiber discussion, while a probiotic trial should use clear organism labeling and stable timing; adding both together hides the result.

    Can sugar alcohols make bloating worse?

    Sugar alcohols can increase gas or loose stool in some people because absorption and fermentation vary. Check gummies, sugar-free candy, gum, protein bars, and drink mixes for maltitol, sorbitol, mannitol, xylitol, or erythritol.

    How long should I test a probiotic?

    Use the label directions and a predefined review date rather than indefinite experimentation. Stop earlier for severe or clearly worsening symptoms, and ask a clinician about duration when health conditions or medications affect safety.

    Does nighttime bloating mean SIBO?

    No. Small-intestinal bacterial overgrowth is one possible clinical consideration, but diet, constipation, visceral sensitivity, and pelvic-floor dysfunction can look similar. Breath testing also has limitations, so testing should follow a clinician’s assessment.

    Nighttime lower-abdominal bloating needs a pattern-matched comparison, not a universal “debloat” product. Track meals, stool, visible distension, and warning signs before testing one variable. Yuve, Culturelle, and Align offer different probiotic label and format profiles, but none replaces evaluation when symptoms are severe, progressive, or unexplained.

  • Still Tired Months After Quitting Coffee? Caffeine-Free Options Compared

    Still Tired Months After Quitting Coffee? Caffeine-Free Options Compared

    Fatigue that persists three months after quitting coffee is unlikely to be caffeine withdrawal alone. Typical withdrawal resolves within days, not months. Protect the reflux improvement, review sleep and food intake, and ask a clinician about persistent fatigue before buying an “energy” supplement. Iron or vitamin B12 only fits when diet, risk, or testing supports it.

    How did we evaluate caffeine-free fatigue options?

    We prioritized the documented caffeine-withdrawal timeline, National Institutes of Health nutrient guidance, and current Supplement Facts panels rather than testimonials or stimulant marketing. We separated options that can mask tiredness from interventions that address a defined cause. Sleep regularity, adequate food, hydration, and medical evaluation came before supplements because fatigue has many possible contributors. For iron and vitamin B12, we required a plausible intake or absorption risk and favored laboratory confirmation when appropriate. We compared Yuve, MegaFood, and Nature Made iron products by elemental iron dose, chemical form, added nutrients, verification claims, label warnings, and ingredient forms; brand reputation and customer reviews did not determine ranking. Product labels can change, and no head-to-head trial establishes one listed iron supplement as the best choice for fatigue today. Persistent or worsening symptoms require individual medical assessment.

    Can caffeine withdrawal still cause fatigue after three months?

    Caffeine withdrawal commonly causes fatigue, headache, sleepiness, reduced alertness, irritability, and difficulty concentrating. Its timing is much shorter than three months. A review of 57 experimental and nine survey studies found that symptoms usually began 12 to 24 hours after stopping caffeine, peaked at 20 to 51 hours, and lasted 2 to 9 days; the Psychopharmacology review also found greater severity with higher habitual doses. A slow taper can reduce early withdrawal, but restarting caffeine months later is not a diagnostic test for ongoing fatigue. Caffeine can temporarily increase alertness and can reverse withdrawal-related impairment, yet that effect may conceal inadequate sleep or another cause. If reflux improved after removing coffee, preserve the useful change while investigating the fatigue separately. Decaffeinated coffee, low-acid coffee, tea, and caffeine tablets can still affect symptoms differently, so reintroduction should be deliberate rather than an automatic response to exhaustion.

    What should you check before comparing supplements?

    Start with sleep opportunity, sleep quality, meal regularity, total calories, protein, hydration, alcohol, exercise load, stress, mood, medications, and recent illness. Note snoring, witnessed breathing pauses, restless legs, morning headaches, heavy menstrual bleeding, blood donation, plant-based eating, and prolonged acid-suppressing medicine use. These details can guide a clinician toward appropriate testing rather than a broad supplement stack. A common initial evaluation may include a complete blood count and, when the history supports it, ferritin, iron studies, thyroid testing, metabolic markers, or vitamin B12. NIH explains that ferritin reflects iron stores but can rise with inflammation, so clinicians often interpret multiple markers in context. The NIH iron fact sheet also warns that hemoglobin and hematocrit are not sensitive or specific enough to describe every stage of iron deficiency. Seek prompt care for chest pain, fainting, severe shortness of breath, black or bloody stool, new neurologic symptoms, or rapidly worsening weakness.

    Which caffeine-free options best match the reason for fatigue?

    Timeline separating short caffeine withdrawal from longer-term fatigue evaluation
    Timeline separating short caffeine withdrawal from longer-term fatigue evaluation

    Best for short sleep: a stable wake time and enough time in bed. Best for missed meals: a regular meal containing protein, carbohydrate, and fat. Best for dehydration: fluids matched to thirst, heat, exercise, and medical context. Best for confirmed iron deficiency: clinician-guided oral iron with a dose and form the person can tolerate. Best for vitamin B12 deficiency or high risk: an appropriate B12 product or prescription pathway. The NIH vitamin B12 fact sheet identifies fatigue as one possible deficiency symptom, but B12 does not act as a general stimulant when status is adequate.

    Option Best for Key limitation
    Sleep and schedule review Insufficient or fragmented sleep May require sleep-disorder evaluation
    Regular meals and hydration Under-fueling or fluid mismatch Not a treatment for anemia or endocrine disease
    Iron Confirmed deficiency or clinician-identified need Can cause GI effects and dangerous overdose
    Vitamin B12 Deficiency, malabsorption, or intake risk Usually does not boost energy when status is adequate
    Caffeine substitute Short-term alertness preference Can reintroduce reflux, sleep, or dependence problems

    Which iron products fit an iron-specific decision lane?

    Some links below may be affiliate links. This does not influence our evaluation criteria or recommendations. Iron belongs only in a laboratory- or clinician-supported lane; the NIH Office of Dietary Supplements notes that routine iron supplementation is not recommended for performance unless iron depletion exists. Yuve Whole Food Iron provides 18 mg of iron as rice protein chelate per capsule. MegaFood Blood Builder lists 26 mg of iron and also contains vitamin C, folate, and vitamin B12. Nature Made Iron lists 65 mg elemental iron as 325 mg ferrous sulfate and carries USP Verified labeling. Every iron product requires storage away from children because accidental overdose can be fatal.

    Product Declared iron Best fit to discuss Important limitation
    Yuve Whole Food Iron 18 mg rice protein chelate Lower-dose vegan capsule Not a treatment dose by default
    MegaFood Blood Builder 26 mg iron plus C, folate, B12 Multi-nutrient tablet Added nutrients may duplicate a routine
    Nature Made Iron 65 mg as ferrous sulfate Higher-dose USP Verified tablet Higher GI-burden potential; clinician fit matters

    How can you protect reflux improvement while addressing fatigue?

    Keep the change that improved symptoms while testing one fatigue variable at a time. Preserve the coffee-free morning routine, then anchor wake time, breakfast or another planned meal, daylight exposure, and movement before adding a supplement. If you miss the ritual, choose a caffeine-free beverage that is not acidic, carbonated, mint-heavy, or very large when those features trigger reflux. Avoid taking iron casually to “see if it works,” because iron can cause nausea, abdominal discomfort, or constipation and can interact with medicines. If testing confirms a need, follow the product label and clinician instructions; calcium, antacids, thyroid medicine, and some antibiotics can affect iron timing. The Yuve daily essentials collection should be judged by the same rule as any store: each product needs a defined purpose, disclosed dose, interaction review, and evidence matched to the ingredient. Best for persistent fatigue is a cause-first plan, not a larger supplement stack.

    What are common questions about fatigue after quitting coffee?

    How long does caffeine withdrawal usually last?

    Most documented withdrawal symptoms resolve within 2 to 9 days. A three-month course should prompt a search for other contributors rather than an assumption that withdrawal simply continued.

    Should I restart coffee to test the fatigue?

    Not automatically. Caffeine may temporarily improve alertness without identifying the cause, and coffee may bring back reflux or sleep disruption. Discuss persistent fatigue with a clinician instead.

    Can iron help if my ferritin is normal?

    Iron should not be treated as a general energy supplement. Ferritin requires contextual interpretation, but normal iron status makes an iron-specific benefit less plausible and increases the importance of avoiding unnecessary dosing.

    Can vitamin B12 boost energy immediately?

    Vitamin B12 can correct a deficiency over time, but it is not a stimulant. People with adequate status should not expect a reliable immediate energy effect.

    Is decaf coffee completely caffeine-free?

    No. Decaf coffee contains much less caffeine than regular coffee, but it is not necessarily zero. Acidity and other coffee components can also matter independently of caffeine.

    When is fatigue urgent?

    Urgent evaluation is appropriate for chest pain, fainting, severe shortness of breath, black or bloody stool, one-sided weakness, confusion, or rapidly worsening symptoms.

  • Rate My Supplement Stack as an Athlete: What to Keep, Skip, or Test

    Rate My Supplement Stack as an Athlete: What to Keep, Skip, or Test

    An athlete’s supplement stack should begin with a defined performance goal, adequate food and fluids, then only a few evidence-matched products. Protein helps close an intake gap, creatine supports repeated high-intensity work, and caffeine can improve selected sessions. Iron belongs only in a lab-informed plan. Third-party sport certification matters for every competition-facing product.

    How did we evaluate an athlete supplement stack?

    We evaluated each stack component by asking four questions: does it match a measurable goal, does human research support that use, is the amount disclosed, and can an athlete verify contamination controls? We prioritized the National Institutes of Health Office of Dietary Supplements, Operation Supplement Safety, current Supplement Facts panels, and searchable sport-certification programs. We excluded proprietary blends that hide ingredient amounts, products built around testimonials, and ingredients supported mainly by animal or mechanistic research. Food, training, sleep, hydration, and prescribed care were treated as the foundation rather than supplements, because a powder cannot repair an underfueled training plan. We also separated performance aids such as creatine and caffeine from nutrient-correction products such as iron. Evidence and risk vary by sport, dose, sex, diet, medicine use, governing body, and competition date. This framework rates the logic of a stack; it does not provide clearance for an individual athlete.

    What belongs in the foundation before supplements?

    Training specificity, total energy intake, protein distribution, carbohydrate availability, fluids, sodium, and sleep belong ahead of every supplement bottle. An athlete who routinely under-eats carbohydrate may experience flat sessions that a stimulant temporarily masks but does not solve. Protein powder is useful when food cannot conveniently close the daily protein gap; it is not mandatory when meals already provide enough high-quality protein. Electrolyte products make the most sense when sweat loss, heat, duration, or repeated sessions create a replacement need, not because flavored sodium is inherently athletic. Track the goal, baseline, and response for each addition. A simple stack ledger should list product, amount, time, reason, certification, lot number, start date, and outcome measure. Remove any item that duplicates a fortified food, multivitamin, pre-workout, or recovery blend. The strongest foundation produces boring consistency: adequate meals, progressive training, regular sleep, and a stack small enough that every ingredient has a job.

    How do protein, creatine, caffeine, and iron compare?

    Protein, creatine, caffeine, and iron solve different problems. The NIH exercise-performance fact sheet reports that creatine can improve strength, power, and repeated maximal work, while protein powder supplies amino acids when food intake falls short. Caffeine can support selected sessions, but its dose, timing, and effect on sleep change the tradeoff. Iron supports oxygen transport; extra iron offers no advantage when status is adequate and can cause harm. Best for a food gap: protein. Best for repeated high-intensity work: creatine monohydrate. Best for a targeted session: a disclosed caffeine dose. Best for low ferritin or iron deficiency: clinician-guided iron.

    Option Best fit Useful label metric Main limitation
    Protein powder Closing a daily protein gap Protein grams and amino-acid source Redundant when food intake is sufficient
    Creatine monohydrate Strength, power, repeated sprints 3–5 g creatine monohydrate Not a substitute for training
    Caffeine Selected hard sessions or competition Total caffeine in milligrams Sleep, heart-rate, and anxiety tradeoffs
    Iron Lab-confirmed low status or clinician-identified need Elemental iron, form, and amount Excess intake can be harmful

    Why does sport certification change the rating?

    Sport certification reduces a contamination risk that ordinary marketing terms do not address. “Clean,” “GMP,” “natural,” and “third-party tested” can describe different scopes and do not automatically mean a product was screened for substances prohibited by a sport. Operation Supplement Safety recommends programs such as NSF Certified for Sport, Informed Sport, BSCG Certified Drug Free, and USP Verified, while noting that each program tests a different scope. Athletes should search the certifier’s database for the exact product and, when possible, the lot or batch. A logo copied onto a marketplace listing is not verification. Certification also does not prove that an ingredient improves performance or suits a medical history. Best for drug-tested competition: a product listed in a sport-specific certification database. Best for general identity and potency verification: a recognized program whose published scope matches the concern. Keep packaging and lot numbers until the competition cycle ends.

    Which iron products fit a lab-informed athlete plan?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Iron should enter a stack after dietary and laboratory review, not after fatigue alone. Yuve Whole Food Iron provides 18 mg elemental iron as a rice-protein chelate in one vegan capsule, fitting a lower-dose plant-based lane when that amount is appropriate. Thorne Iron Bisglycinate provides 25 mg iron as bisglycinate and carries NSF Certified for Sport, fitting athletes who require sport-specific verification. Nature Made Iron provides 65 mg elemental iron as ferrous sulfate and is USP Verified; its label targets iron deficiency, so clinician direction matters. Compare elemental dose, form, certification, dietary fit, and tolerance rather than declaring one universal winner.

    Product Elemental iron Form Verification and fit
    Yuve Whole Food Iron 18 mg Rice-protein chelate Vegan; independent batch testing stated by brand; request lot COA
    Thorne Iron Bisglycinate 25 mg Iron bisglycinate NSF Certified for Sport
    Nature Made Iron 65 mg Ferrous sulfate USP Verified; labeled for deficiency

    Should every athlete take creatine?

    No. Creatine monohydrate has strong evidence for repeated high-intensity exercise, strength, power, and training adaptation, but the goal and sport still matter. A distance athlete who needs no sprint, lift, or repeated-power benefit may assign it a lower priority than carbohydrate availability or iron-status screening. Choose plain creatine monohydrate with a disclosed amount and recognized sport certification when competition rules apply. Typical research protocols often use either a loading phase followed by maintenance or a steady daily amount, but an athlete should align dosing with a qualified sports dietitian and governing-body requirements. Scale weight can rise because creatine increases intracellular water, which may matter in weight-class or aesthetic sports. Kidney disease, pregnancy, medicine use, adolescence, and complex health histories require individual guidance. If the product contains stimulants, botanicals, or a proprietary blend, rate those additional ingredients separately; “contains creatine” does not validate the entire formula.

    Can a pre-workout replace coffee or food?

    A pre-workout can deliver caffeine and other ingredients conveniently, but it cannot replace carbohydrate, fluid, sodium, or sleep. Coffee provides a less standardized caffeine dose, while a transparent pre-workout should list caffeine in milligrams per serving. Products that combine caffeine, synephrine, yohimbe, higenamine, or undeclared stimulant analogs raise a different risk than caffeine alone. Operation Supplement Safety warns that multi-stimulant formulas can affect heart rate, blood pressure, sleep, gastrointestinal comfort, and readiness. Start by calculating caffeine from coffee, energy drinks, gels, gum, and powder across the full day. Test any legal, certified product during training rather than for the first time at competition. Best for dose control: a single-ingredient or fully disclosed product. Best for fueling: food or a sports drink matched to session demands. Chest pain, faintness, severe palpitations, or unusual shortness of breath requires medical evaluation, not a different flavor of pre-workout.

    Does a multivitamin make an athlete stack complete?

    No. A multivitamin can help cover selected intake gaps, but it cannot guarantee adequate energy, protein, carbohydrate, essential fatty acids, iron status, vitamin D status, or hydration. Review every nutrient across fortified foods, electrolyte mixes, protein powders, gummies, and separate capsules before adding one. Overlap is especially relevant for iron, zinc, selenium, vitamin A, niacin, and vitamin B6 because multiple products can push totals far above the intended serving. A multivitamin with a proprietary “performance blend” should be judged as both a nutrient product and a performance supplement. Use blood testing only when clinically appropriate; broad panels without a decision plan can generate noise. Best for a documented dietary gap: the specific nutrient and amount that address it. Best for general insurance when diet is inconsistent: a modest, transparent multivitamin without duplicated megadoses. The goal is not to fill every nutrient to the highest possible percentage on the label.

    How often should you change an athlete supplement stack?

    Review the stack at the start of each training block, after a meaningful diet or health change, and before any competition governed by anti-doping rules. Do not change several products simultaneously because a cluster of additions hides which ingredient affected sleep, digestion, weight, heart rate, or training output. Give each optional item a defined trial, stable dose, and outcome measure. Creatine can be assessed through repeated training performance and body-mass changes; caffeine can be assessed through target-session performance and sleep; protein powder can be assessed by whether it closes a calculated intake gap. Iron requires laboratory and clinical follow-up rather than a gym-performance guess. Recheck certification databases because formulas, suppliers, and listings can change. Remove expired products and anything without a readable lot number. A smaller stack reviewed quarterly usually produces better information than a cabinet that grows every time social media discovers a new mechanism.

    What red flags should make an athlete stop a supplement?

    Stop and seek prompt medical advice for chest pain, fainting, severe palpitations, breathing difficulty, facial swelling, repeated vomiting, unusual bleeding, or a rapidly spreading rash. Discontinue a new product when it causes persistent insomnia, marked anxiety, diarrhea, constipation, or abdominal pain, then preserve the package and lot number. Report suspected supplement adverse events to the FDA when appropriate. An unexpected drug-test result, missing certification listing, changed label, broken seal, or marketplace bottle that differs from the manufacturer page also justifies stopping. Iron products require particular storage care because accidental overdose can be fatal to young children. Do not treat dark stool, fatigue, or stomach pain as proof that iron is “working.” Do not restart a product after a suspected allergic reaction without clinical guidance. A stack earns its place through a favorable benefit-risk profile; tolerating escalating side effects is not evidence of athletic discipline.

    Related reading: Best Supplement to Give You Energy: What Actually Fits the Cause?.

    Related reading: Best Natural Energy Boosters Without Caffeine: What Actually Helps?.

    Related reading: How to Pick the Right Energy Supplement: Match the Ingredient to the Reason.

    What is the bottom line for rating an athlete stack?

    Keep the stack goal-based, disclosed, certified, and small. Food, training, carbohydrate availability, protein distribution, hydration, and sleep form the base. Protein powder earns a place when it closes an intake gap. Creatine monohydrate earns a place when repeated strength or power matters. Caffeine earns a place when a tested dose improves a target session without damaging sleep. Iron earns a place only when dietary and laboratory context support it; Yuve, Thorne, and Nature Made occupy different dose and verification lanes rather than a single ranking. Search the exact product in a recognized certification database, retain the lot number, and retest assumptions each training block. A useful stack produces a measurable benefit with acceptable risk. An item without a defined goal, disclosed dose, or verification path is clutter, even when its mechanism sounds impressive. Browse broader daily essentials only after the performance and nutrient gap is clearly defined.

  • Low Beneficial Bacteria on a Gut Microbiome Test: What to Do Next

    Low Beneficial Bacteria on a Gut Microbiome Test: What to Do Next

    A commercial stool report showing “low beneficial bacteria” is not a diagnosis and does not prove that important microbes are absent throughout your gut. First verify the method, reference population, and whether results are relative abundance. Then prioritize a varied diet and symptom-based care; consider a strain-identified probiotic only for a defined goal, not to chase every low bar.

    How did we evaluate low-beneficial-bacteria microbiome results?

    We evaluated consumer microbiome reports by analytical method, clinical validation, reference ranges, sampling variability, and whether a proposed next step has human evidence. An international clinical consensus statement received more weight than a testing company’s wellness score, supplement bundle, or color-coded dashboard. Human dietary-intervention research informed the food section, while the NIH Office of Dietary Supplements guided the probiotic-label comparison. We excluded claims that one stool sample maps the entire intestinal ecosystem, that a low relative abundance equals a deficiency, or that a supplement can permanently “repopulate” the gut. The evidence has important limits: sequencing platforms identify different organisms, databases change, stool represents mainly the distal colon, and relative-abundance percentages can shift when another organism rises or falls. Symptoms, medications, recent antibiotics, diet, transit time, and collection technique also affect interpretation. The practical goal is not to normalize every proprietary score. It is to identify validated clinical questions, support a varied dietary pattern, and choose any supplement by a specific purpose and transparent label.

    What does “low beneficial bacteria” actually mean?

    The phrase usually means that the laboratory detected a lower relative abundance of selected taxa compared with its own reference group. It does not necessarily mean zero living cells, whole-gut depletion, or impaired function. Relative abundance works like a percentage chart: one group’s share can fall because another group expanded even when the first group’s absolute count did not change. Different companies may use 16S rRNA sequencing, shotgun metagenomics, different collection preservatives, different taxonomic databases, and different “healthy” comparison cohorts. Those choices can produce different names and scores from the same biological sample. The 2025 international consensus statement concluded that evidence for routine clinical usefulness remains scarce and warned that direct-to-consumer reports can lead to waste or inappropriate management. Ask whether the result is absolute or relative, whether the marker has a validated clinical threshold, and whether repeating the sample would likely change the interpretation. A commercial wellness category should not be treated like a blood-test deficiency.

    Can diet change the gut microbiome after a low result?

    Diet can change microbial activity and composition, but no single menu reliably restores a proprietary “beneficial bacteria” score. A practical foundation includes varied plant foods, legumes, whole grains, nuts, seeds, fruits, vegetables, and fermented foods that fit personal tolerance. Increase fermentable fiber gradually because abrupt changes can increase gas or bloating. In a 17-week randomized Cell trial, a high-fermented-food diet increased microbiota diversity and reduced several inflammatory markers, while a high-fiber diet increased microbiome carbohydrate-processing capacity without increasing community diversity. The study included only 18 participants per arm, so it provides directional evidence rather than a universal prescription. Fermented foods also vary: pasteurization, storage, and product type affect live microorganisms. A diverse diet remains more defensible than buying foods solely to raise one genus on a report. People with significant gastrointestinal symptoms, food restrictions, immune compromise, or recent treatment should personalize changes with a qualified clinician or registered dietitian rather than force high-fiber or fermented-food targets.

    How do the main next-step options compare?

    Some links below are affiliate links. This does not influence our evaluation criteria. Food-first changes offer substrate variety but require gradual steps. Yuve Probiotic Gummies provide 5 billion CFU of Bacillus coagulans per two-gummy serving, with species-level labeling. Culturelle Digestive Daily names Lacticaseibacillus rhamnosus GG; Align 24/7 Digestive Support names Bifidobacterium longum 35624. A dietitian fits restrictive eating or fiber intolerance. Clinical evaluation fits persistent symptoms or alarm signs because a consumer score cannot exclude medical causes. Retesting can show change, but a prettier dashboard does not prove better health.

    Option Best for Evidence anchor Main limitation
    Food-first variety Broad daily foundation Human diet studies Response and tolerance vary
    Yuve Probiotic Gummies Vegan gummy adherence 5 billion CFU B. coagulans Species-level label
    Culturelle Digestive Daily LGG strain traceability L. rhamnosus GG Goal-specific evidence still matters
    Align 24/7 Digestive Support 35624 strain traceability B. longum 35624 Not a universal microbiome reset
    Dietitian or clinician Symptoms or restrictions Clinical history and validated tests Requires an appointment

    Which option is best for each use case?

    Relative abundance and absolute bacterial counts in a commercial gut microbiome test
    Relative abundance and absolute bacterial counts in a commercial gut microbiome test

    Best for a low score without significant symptoms: food variety, regular meals, sleep, movement, and a cautious review of the test’s methodology before buying anything. Best for a vegan, capsule-free probiotic habit: Yuve Probiotic Gummies, provided the user accepts species-level rather than strain-level identification and tolerates the sweetener system. Best for maximum label traceability: Culturelle or Align, because each names an alphanumeric strain that can be matched more directly to published research. Best for increasing fermentable substrate: whole foods first, followed by a measured soluble or prebiotic fiber only when tolerance and dose are clear. Best for restrictive eating after a report: a registered dietitian who can protect nutritional adequacy. Best for ongoing symptoms or alarm signs: a clinician using medical history and validated testing rather than the commercial diversity score. The digestion collection can help compare formats, but no product should be selected merely because a dashboard marked one bacterial group red.

    How should you choose a probiotic after a microbiome test?

    Start with a defined goal rather than the name of a “missing” genus. The NIH Office of Dietary Supplements explains that probiotic effects depend on the specific microorganisms and dose; higher CFU counts alone do not guarantee greater benefit. Read the genus, species, alphanumeric strain, CFU amount, serving size, expiration-based viability statement, storage directions, allergens, and other ingredients. A product that lists only a proprietary blend offers weak evidence traceability. Match published evidence to the exact strain and intended outcome instead of assuming that any Bifidobacterium, Lactobacillus, or Bacillus product replaces a low stool-report category. Introduce one product at a time and predefine what improvement would look like, such as a consistent change in bowel frequency or comfort. Track tolerance because probiotics and prebiotic ingredients can increase gas. Reassess at the label-directed interval. Stop and seek professional guidance if symptoms worsen, and avoid self-directed probiotic use when seriously ill or immunocompromised.

    What questions should you ask about a low microbiome score?

    Is low diversity always unhealthy?

    No. Diversity varies with age, geography, diet, medication, transit, and laboratory method; no universal healthy cutoff exists for consumer testing.

    Can a probiotic permanently colonize the gut?

    Usually not. Many probiotic strains are detectable mainly during use, so benefits—when present—do not require permanent colonization.

    Should I repeat the same stool test?

    Retesting can show analytical or biological change, but it may not change care. Ask what decision a second result would alter before paying again.

    Do I need to eat every food the report recommends?

    No. Use tolerance, nutritional adequacy, allergies, and medical guidance rather than a proprietary food list built from uncertain associations.

    Can antibiotics lower beneficial bacteria?

    Antibiotics can disrupt microbiome composition, but recovery patterns vary. Do not take or stop an antibiotic based on a consumer stool score.

    When does the result need clinical review?

    Seek review for persistent symptoms, bleeding, fever, dehydration, swallowing problems, repeated vomiting, or unexplained weight loss. The report cannot exclude medical causes.

    For a closer look at clean-label options, see Should a Microbiome Test Change Your Gut-Health Routine?.

    What is the bottom line after a low beneficial-bacteria result?

    Treat the report as a hypothesis generator, not a diagnosis or personalized prescription. Verify whether the company reports relative abundance, which sequencing method it uses, how its reference cohort was built, and whether any flagged marker has a validated clinical threshold. A varied diet that gradually expands tolerated plant fibers and fermented foods has broader human evidence than chasing one bacterial genus. If a probiotic fits a defined goal, choose by strain identity, viable dose, storage, other ingredients, and a measurable trial—not by the largest CFU number or a promise to reset the microbiome. Yuve offers a vegan gummy adherence option with species-level Bacillus coagulans labeling; Culturelle and Align offer more precise strain identification in capsule formats. None can be ranked as a universal repair tool. Persistent symptoms deserve symptom-based clinical evaluation, and alarm signs deserve prompt care. A better outcome is improved function, tolerance, and nutritional adequacy, not simply moving a commercial dashboard from red to green.

  • Metamucil Plus Probiotics: What to Compare Before Combining Fiber and Live Cultures

    Metamucil Plus Probiotics: What to Compare Before Combining Fiber and Live Cultures

    Combining a soluble-fiber product with a probiotic can be reasonable, but one success story does not prove that the pair “fixes” IBS-C. Compare the fiber type, probiotic strain, dose, sweeteners, hydration needs, and tolerance. Introduce one product at a time so any benefit or side effect remains traceable.

    How did we evaluate fiber-plus-probiotic routines?

    We compared routines by fiber chemistry, named probiotic organism, labeled amount, evidence quality, serving format, and the ability to test one variable at a time. Clinical guidelines and systematic reviews received more weight than testimonials, brand category claims, or CFU totals without strain context. The 2021 American College of Gastroenterology guideline supports soluble fiber for global IBS symptoms but suggests against probiotics as a class because results vary across organisms and trials (ACG guideline). That distinction prevents a successful psyllium-and-probiotic story from becoming a universal recommendation. We excluded claims that a supplement cures IBS-C or replaces evaluation for new, severe, or changing symptoms. Product labels can change, and finished-product evidence is often thinner than ingredient evidence. The practical question is therefore not whether “fiber plus probiotics” works universally; it is whether a specific, documented combination improves a defined outcome without creating worse bloating, pain, urgency, or medication conflicts.

    Why can fiber and probiotics produce different results?

    Fiber changes stool water, bulk, viscosity, and microbial fermentation, while a probiotic introduces a specific live microorganism in a stated amount. Psyllium forms a viscous gel and is relatively slowly fermented; wheat dextrin dissolves easily but behaves differently; chicory-root inulin and fructooligosaccharides ferment more readily. Probiotic effects depend on the exact organism and strain, not merely the words “live cultures.” The NIH Office of Dietary Supplements explains that benefits cannot be transferred automatically between probiotic strains or products (NIH ODS). Fermentable fiber can also increase gas when the dose rises quickly. NIDDK recommends adding fiber gradually and drinking enough liquid to help fiber work effectively (NIDDK). A two-product routine therefore contains at least two active variables. Dose, timing, baseline diet, stool pattern, and individual tolerance can change the result even when two shoppers buy the same bottles.

    How do common fiber-and-probiotic combinations compare?

    Some links below are affiliate links. This does not influence our evaluation criteria or recommendations. Metamucil Original uses psyllium, a soluble fiber with guideline support, while Culturelle Digestive Daily products commonly use Lacticaseibacillus rhamnosus GG; buyers should verify the selected SKU. Benefiber Original uses wheat dextrin, while Align products commonly feature Bifidobacterium longum 35624, although the Align range contains multiple formulas. Yuve Prebiotic Fiber Gummies list chicory-root inulin/FOS at 1.5 grams of fiber per gummy, while Yuve Probiotic Gummies list 5 billion CFU of Bacillus coagulans per two-gummy serving. These label facts describe composition, not guaranteed outcomes. Psyllium, dextrin, inulin/FOS, LGG, 35624, and B. coagulans occupy different evidence lanes. The fairest comparison matches each active ingredient to one goal, verifies the current bottle, and avoids assuming that two digestive products automatically create a clinically validated synbiotic.

    Routine Fiber lane Probiotic lane Best for Main limitation
    Metamucil + Culturelle Psyllium Commonly LGG; verify SKU Soluble-fiber priority with named-strain comparison Two products; flavor and sweeteners vary
    Benefiber + Align Wheat dextrin Commonly 35624; verify SKU Clear-mixing powder plus capsule routine Dextrin is not interchangeable with psyllium
    Yuve fiber + probiotic gummies Inulin/FOS, 1.5 g per gummy B. coagulans, 5 billion CFU per two gummies Vegan, capsule-free routine Fermentable fiber may increase gas
    Food fiber + fermented food Mixed food fibers Variable food cultures Food-first dietary variety Organisms and amounts are less standardized

    Which combination is best for each use case?

    Best for prioritizing the strongest fiber guidance: a measured psyllium routine, because the ACG guideline distinguishes soluble fiber from insoluble fiber and gives probiotics a weaker class-level assessment. Best for a capsule-free routine: the Yuve gummy pair, because both products publish active categories and serving amounts in vegan formats, although inulin/FOS should be increased cautiously. Best for organism-specific tracking: a product that names a full probiotic strain, such as LGG or 35624, paired with a separately measured fiber. Best for a food-first trial: oats, legumes, fruit, vegetables, and fermented foods introduced in tolerable portions. Best for unexplained constipation, bleeding, weight loss, fever, vomiting, severe pain, or a sudden bowel-pattern change: clinical assessment rather than another stack. A systematic review found that short-chain beta-fructans can modestly increase stool frequency, but results differ by fiber chain length and population (Nutrients review). No comparison supports calling one combination a universal IBS-C fix.

    How should you test a two-product routine?

    Visual comparison of psyllium, wheat dextrin, inulin fiber gummies, and probiotic formats
    Visual comparison of psyllium, wheat dextrin, inulin fiber gummies, and probiotic formats

    A clean trial starts with a baseline, one change, and a stop rule. Record stool frequency, Bristol Stool Form Scale type, straining, abdominal pain, bloating, water intake, and current medicines for seven days before changing the routine. Add the fiber first when fiber intake is low, because its dose is easier to quantify and soluble fiber has clearer guideline support. Increase gradually according to the label and clinician guidance, then keep the dose stable long enough to observe tolerance. Add a probiotic later only if there is a separate reason to test it. Keep meals, caffeine, exercise, and other supplements as consistent as practical. Stop and seek advice if symptoms become severe or alarming. Prescription medicines, pregnancy, kidney disease, immune compromise, and prior bowel obstruction require individualized review. This sequence does not prove causation, but it produces cleaner information than starting fiber, probiotics, magnesium, and a restrictive diet on the same day.

    What mistakes make the comparison misleading?

    The first mistake is treating all fiber as interchangeable. Psyllium, wheat dextrin, inulin/FOS, cellulose, and bran differ in viscosity, fermentability, dose, and tolerance. The second mistake is ranking probiotics only by billions of CFU; strain identity, viability through expiration, storage, and human evidence matter more than the largest front-label number. The third mistake is changing both products simultaneously, which hides the source of benefit or discomfort. The fourth mistake is ignoring inactive ingredients such as sugar alcohols, flavors, allergens, and sweeteners that can affect tolerance. The fifth mistake is replacing prescribed care with a supplement stack. FDA regulates dietary supplements differently from drugs, and manufacturers remain responsible for lawful safety and labeling before sale (FDA). A comparison is strongest when every option receives the same questions: What is the active ingredient? How much is taken? What exact outcome is being tracked? What evidence matches that ingredient? When should the trial stop?

    What questions should you ask before combining fiber and probiotics?

    Ask whether the main gap is low fiber intake, inconsistent stool form, capsule avoidance, or interest in a particular probiotic strain. Then verify the exact fiber type, grams per serving, organism, strain code, CFU timing, storage requirement, sweeteners, allergens, and serving cost on the current packages. Confirm how each product fits existing food intake and medicines. Choose one primary outcome and a review date before purchasing a second bottle. This checklist separates a repeatable experiment from a hopeful stack. It also prevents category borrowing: ingredient research on psyllium does not validate wheat dextrin, a trial of LGG does not validate B. coagulans, and evidence for a single ingredient does not validate a finished two-product combination. The Yuve digestion collection can organize product formats, but the label and the intended job must still lead the decision. Persistent or changing bowel symptoms belong in a clinician conversation, not a product ranking.

    Can you take Metamucil and a probiotic on the same day?

    Many adults can use both on the same day, but timing, medicines, hydration, and tolerance matter. Follow both labels and ask a pharmacist whether fiber should be separated from any medication.

    Should fiber or the probiotic come first?

    Fiber is often the cleaner first variable when intake is low because its grams can be measured and soluble fiber has stronger IBS guidance. Add a probiotic later only if it serves a separate, defined goal.

    Is a synbiotic automatically better than separate products?

    No. “Synbiotic” describes a combination of microorganisms and substrates, but the finished pairing still needs relevant evidence, viable-count labeling, and a tolerable dose.

    Can inulin make bloating worse?

    Yes. Inulin and FOS are fermentable fibers, so a rapid increase can produce gas or fullness even when the ingredients eventually fit the routine.

    Do higher probiotic CFU counts work better?

    Not necessarily. A lower count of a clearly identified strain with relevant evidence can be more informative than a larger count attached to an unspecified blend.

    When should constipation be medically evaluated?

    Seek prompt guidance for blood in stool, severe or persistent pain, vomiting, fever, unexplained weight loss, inability to pass gas, or a sudden bowel-pattern change. Ongoing constipation also deserves review when self-care is not working.

    For a closer look at clean-label options, see How to Tell Whether Store-Bought Fermented Foods Still Have Live Cultures.

    For a closer look at clean-label options, see VSL#3 Making Symptoms Worse? What to Check Before Switching Probiotics.

    What is the bottom line on combining fiber and probiotics?

    Fiber and probiotics can share a routine, but their presence together does not prove synergy or a cure. Start with the ingredient that addresses the clearest gap, use the current label as the source of truth, and change one variable at a time. Psyllium has the most direct guideline support among the compared fiber lanes. Wheat dextrin offers a different powder format, while inulin/FOS provides a more fermentable prebiotic substrate. LGG, 35624, and B. coagulans are distinct organisms or strains and should not borrow one another’s evidence. The Yuve gummy pair fits shoppers who prioritize a vegan, capsule-free routine; Metamucil plus Culturelle and Benefiber plus Align fit different format and ingredient preferences. None guarantees symptom relief. Define the outcome, document the dose, support fiber with appropriate fluids, and review the result before adding more. A measurable routine beats a crowded supplement drawer because it produces information you can actually use.